Dyslipidemia:
Pathophysiology, Diagnosis & Management
Dr. Eatimad Mahgoub Osheik
LEARNING OBJECTIVES
- Define dyslipidemia
- Understand lipid metabolism
- Interpret lipid profile
- Identify ASCVD risk
- Apply ACC/AHA guidelines
- Choose appropriate therapy
Background
- Lipids are organic water non soluble molecules
- Major types include
- Triglycerides serving as long term energy store
- Phospholipids is a key component of cell membrane
- Cholesterol is vital for building cells, producing hormones (like estrogen, testosterone, vitamin D), and making bile for digestion and brain development
- Cholesterol and triglycerides are carried in the bloodstream by spherical particles called lipoproteins.
A lipoprotein is a complex particle made of lipids like cholesterol , triglycerides and a protein that acts as the body’s transport system for these fats through the bloodstream to cells.
So what is Lipoprotein ?
Structure and Function
- Core: Contains fats like triglycerides and cholesterol.
- Outer Shell: Composed of phospholipids and special proteins called apolipoproteins (like ApoB for LDL, ApoA-I for HDL).
- Function : To carry fats to and from cells throughout the body.
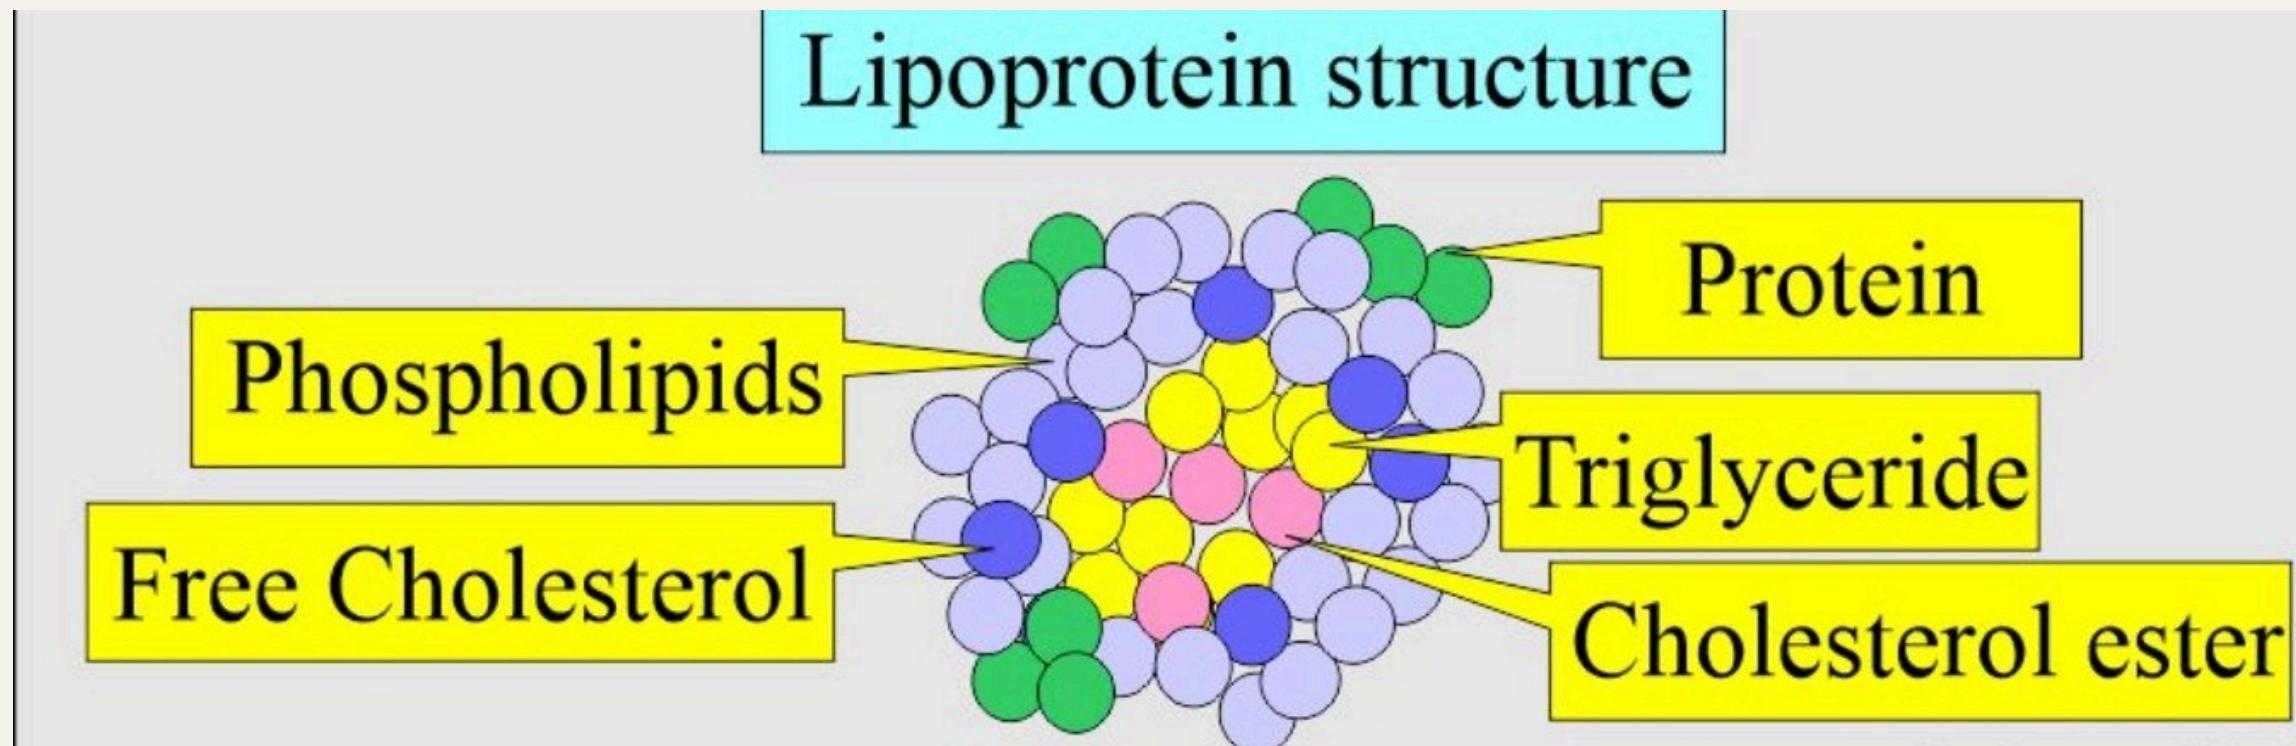
Lipid Metabolism
- Lipoproteins
- Chylomicrons
- VLDL
- IDL
- LDL
- HDL
Here’s a breakdown of major types, density, and size:
- Chylomicrons: Largest and least dense , transport dietary fats from the gut.
- VLDL (Very Low-Density Lipoprotein) Large , low density, carries triglycerides from the liver.
- IDL (Intermediate-Density Lipoprotein): Medium, intermediate density), derived from VLDL.
- LDL (Low-Density Lipoprotein): Smaller, delivers cholesterol to tissues,
- HDL (High-Density Lipoprotein): Smallest , removes cholesterol from tissues, “good” cholesterol.
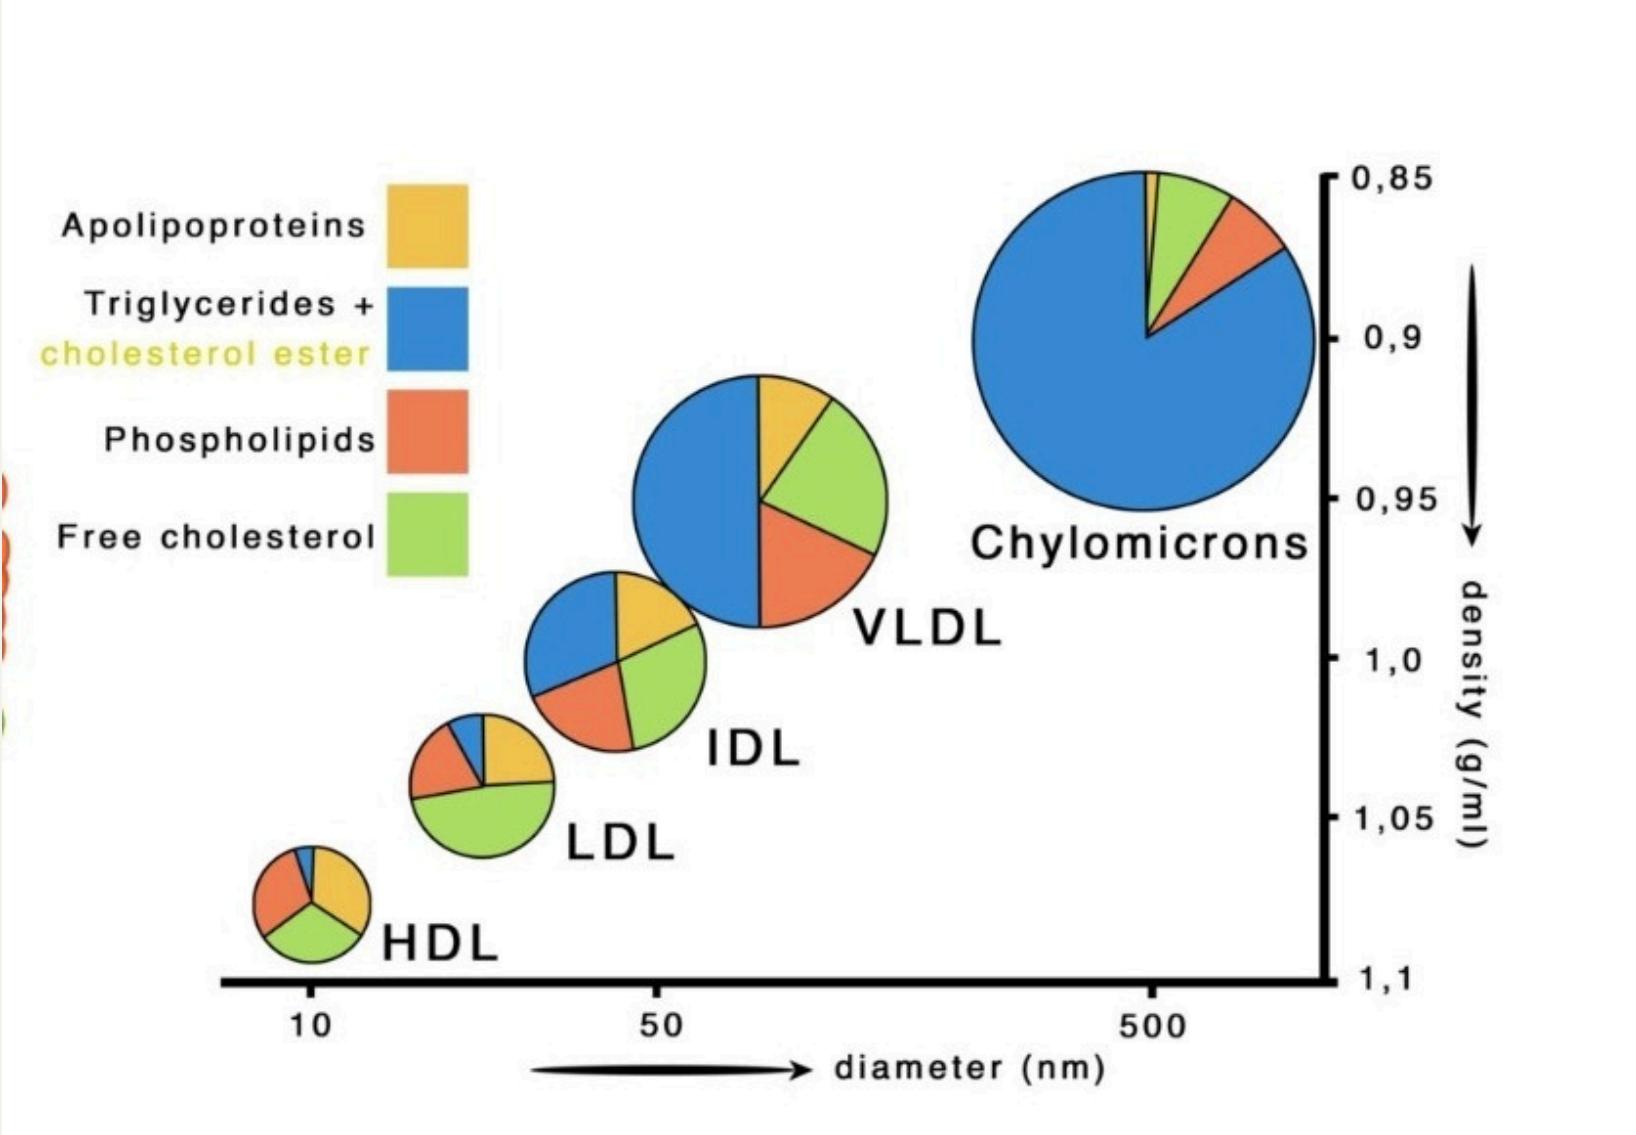
Lipid Metabolism
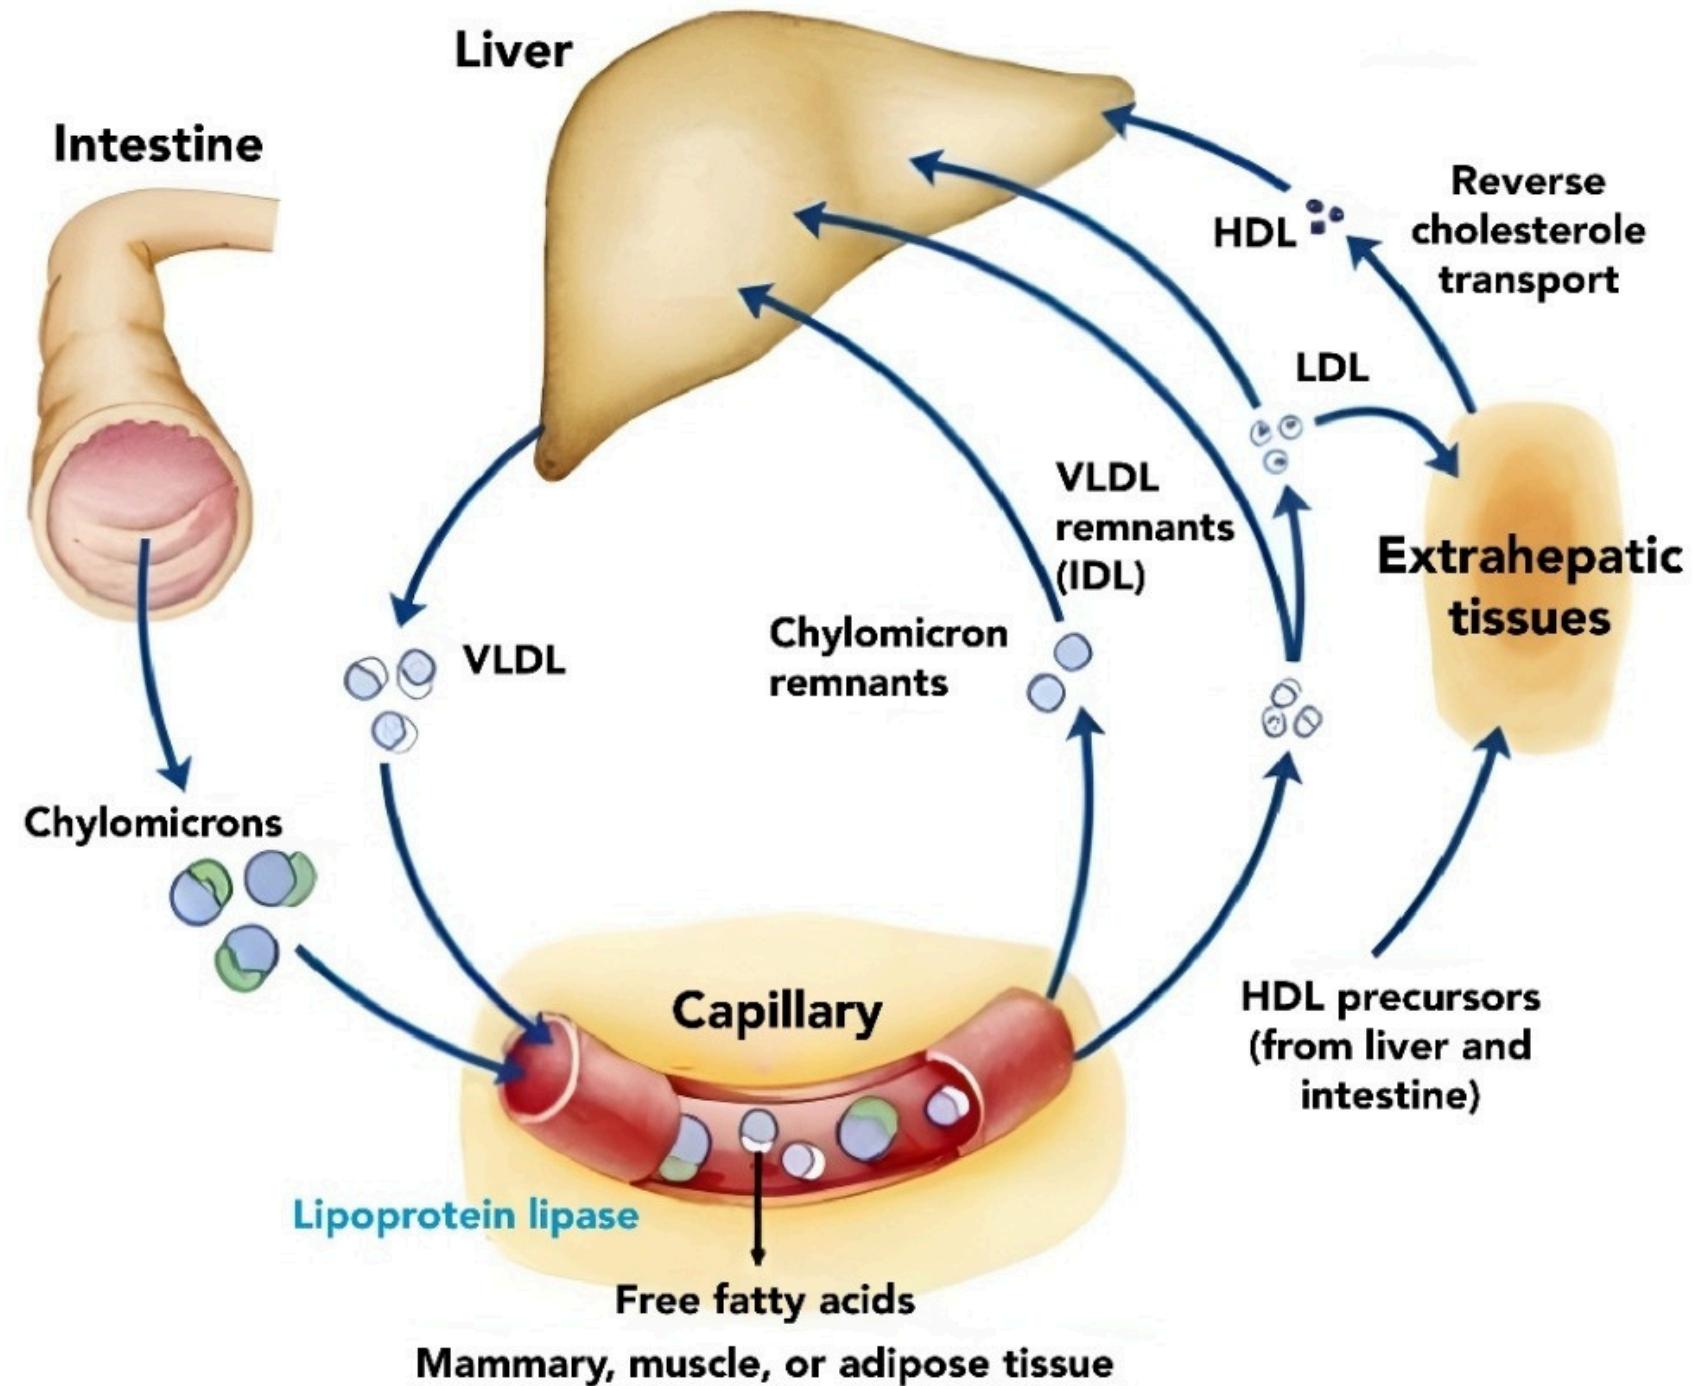
INTRODUCTION
-
Dyslipidemia = abnormal lipid levels in the blood
-
consequence of abnormal Lipoprotein metabolism
-
Major modifiable risk factor for ASCVD
-
Strong association with:
- Coronary artery disease
- Stroke
- Peripheral arterial disease
DYSLIPIDEMIA
Include
- ↑ Low Density Lipoprotein LDL
- ↓ High Density Lipoprotein HDL
- ↑ Triglycerides TG
- Mixed dyslipidemia
Classification of Hyperlipidemia
Primary Hyperlipidemia
secondly Hyperlipidemia
Primary hyperlipidemia
Single or multiple gene defect results in disturbance of LDL, HDL or/ and TG production or clearance
- Type I: Familial Chylomicronemia
- Type IIa: Familial Hypercholesterolemia
- Type IIb: Familial Combined Hyperlipidemia
- Type III: Dysbetalipoproteinemia
- Type IV: Hypertriglyceridemia
- Type V: Mixed Chylomicronemia–VLDL Elevation
| DISEASE | LIPID PROFILE | ETIOLOGY |
|---|---|---|
| Type I Familial hyper-chylomicronemia | ↑Chylomicrons | Deficiency in LPL or apoCII |
| Type IIA Familial hyper-cholesterolemia | ↑LDL | Decreased or no functional LDL receptor expression |
| Type IIB Familial combined hyperlipidemia | ↑ LDL ↑ VLDL | Overproduction of VLDL by liver |
| Type III Familial dysbeta-lipoproteinemia | ↑ IDL | Abnormal apoE |
| Type IV Familial hyper-triglyceridemia | ↑ VLDL | Overproduction and/or impaired catabolism of VLDL |
| Type V Familial mixed hyper-triglyceridemia | ↑Chylomicrons ↑VLDL | Increased production or decreased clearance of VLDL & chylomicrons. |
When to suspect primary hyperlipidemia
- Early onset hyperlipidemia (childhood or young adulthood)
- Strong family history of premature cardiovascular disease
- Very high lipid levels
- LDL-C ≥ 190 mg/dL
- Triglycerides ≥ 500 mg/dL
- Poor response to diet and lifestyle changes
- No secondary cause
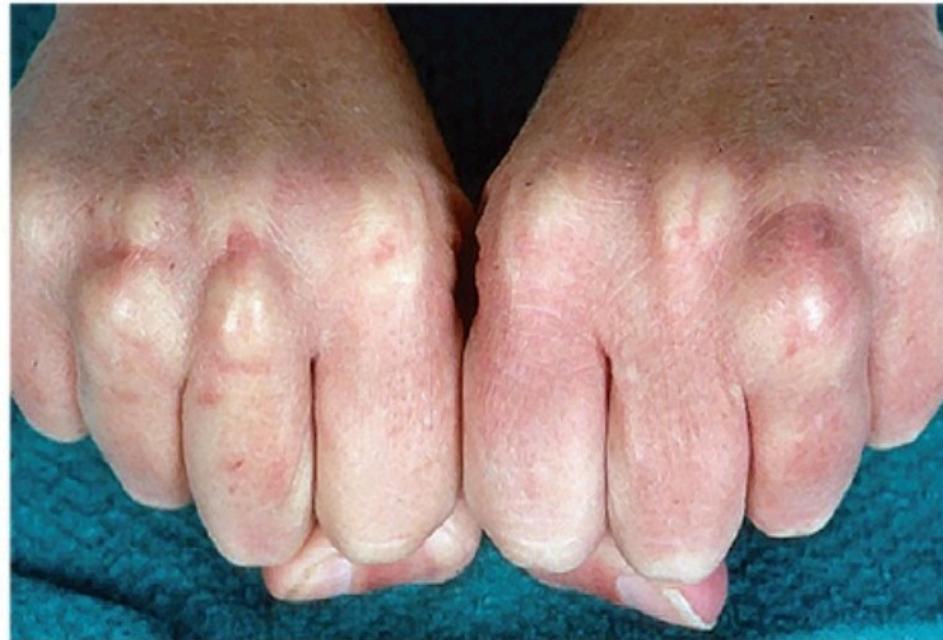
- Characteristic signs: tendon xanthomas, xanthelasma, corneal arcus at young age
Clinical signs of primary hyperlipidemia
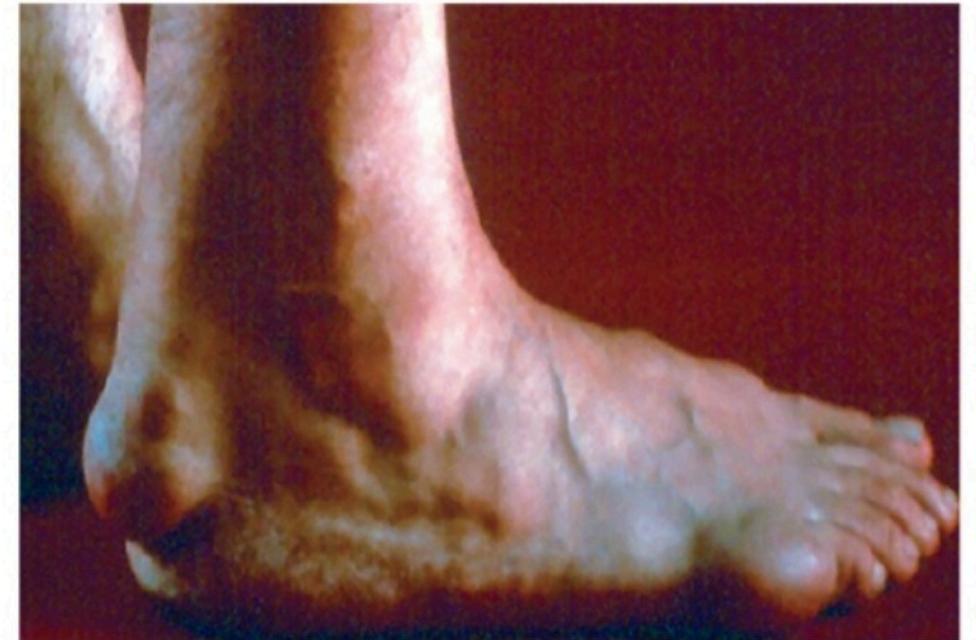
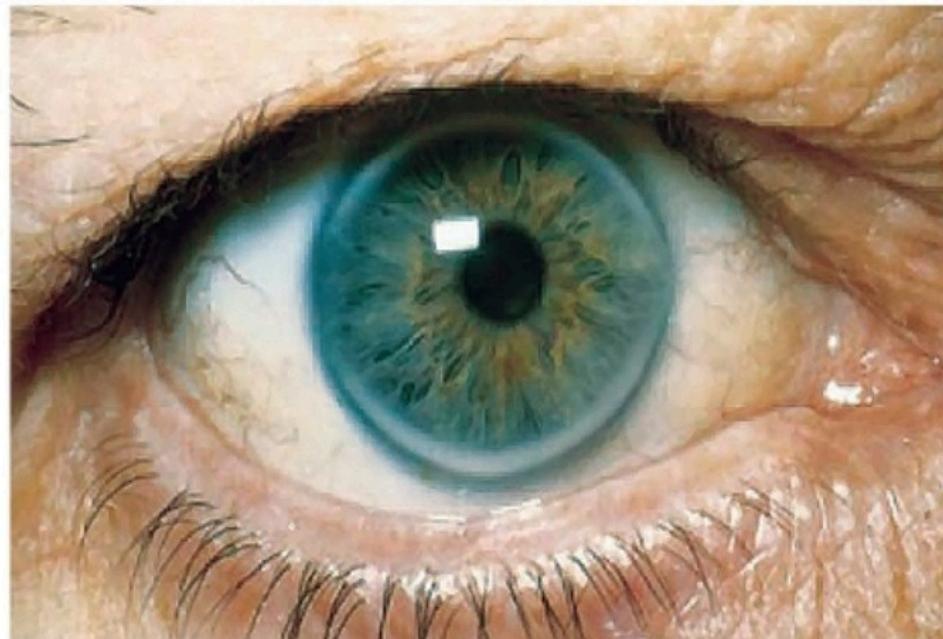
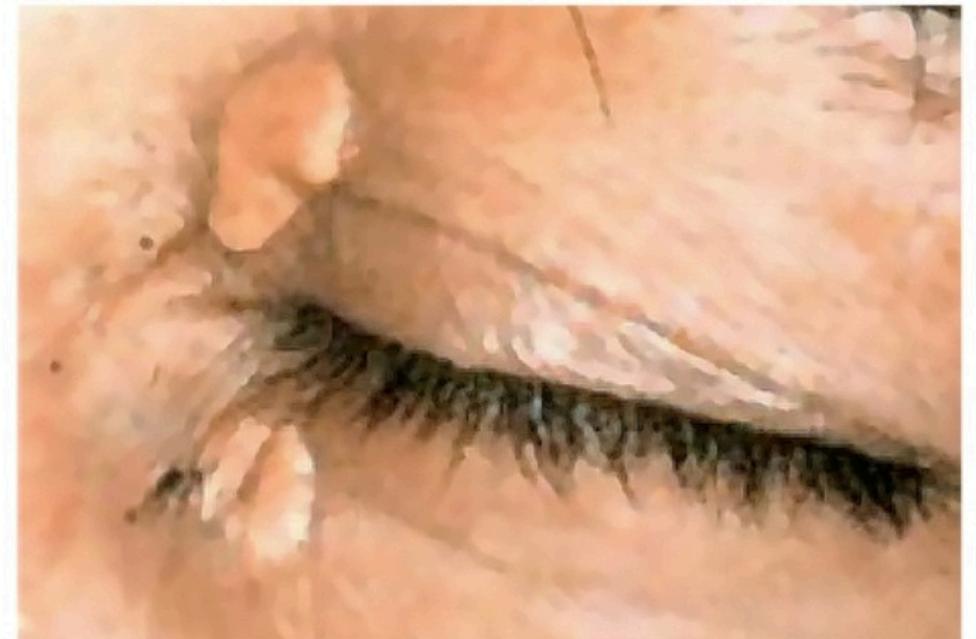
Secondary (acquired) hyperlipidemia
- Endocrine causes diabetes mellitus; hypothyroidism; obesity
- Renal disease—nephrotic syndrome; chronic renal failure
- Hepatic dysfunction; cholestasis
- Medications—thiazide diuretics; β-blockers; oral estrogens; steroids
- Lifestyle factors—excessive alcohol intake; high fat and carbohydrate diets; smoking;
Lipid Profile Interpretation
Normal Values
Total Cholesterol < 200 mg/dL
LDL < 100 mg/dL
HDL. > 40 (men), > 50 (women)
Triglycerides < 150 mg/dl
ASCVD Risk Factors
Nonmodifiable
- Age (men ≥ 45 y; women ≥ 55 y)
- Male sex
- Family history of premature ASCVD
- Race/ethnicity
Modifiable
- Dyslipidemia
- Hypertension
- Diabetes mellitus
- Smoking
- Obesity/metabolic syndrome
ASCVD (KEY CONCEPT)
ASCVD includes
- Coronary artery disease
- Cerebrovascular disease ;Stroke / TIA
- Peripheral arterial disease
ACC/AHA focuses on ASCVD risk, not LDL alone
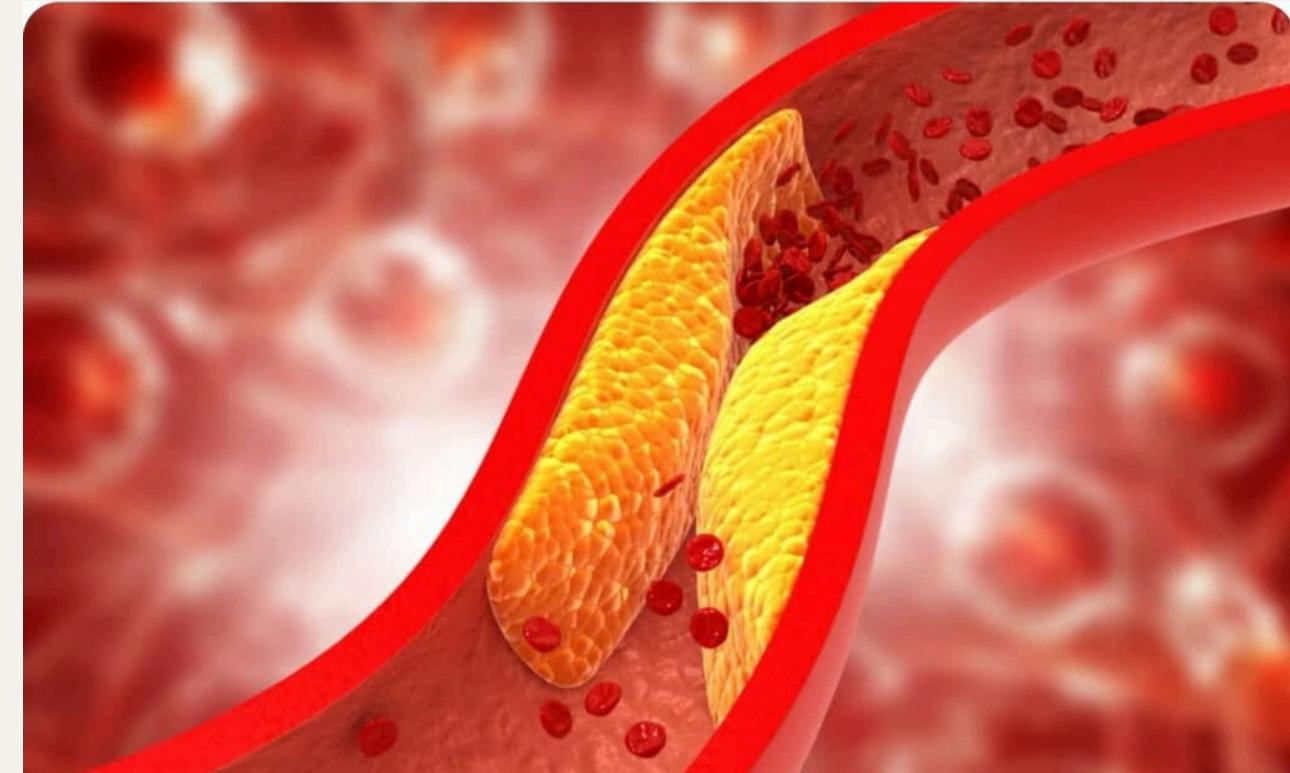
Lipid-Lowering Therapies Summary Table
| Class | Examples | Primary Effect | Use Case | Common Side Effects |
|---|---|---|---|---|
| Statins | Atorvastatin, Rosuvastatin | ↓ LDL, ↓ TG, ↑ HDL | First-line for high CV risk | Muscle pain, liver enzyme elevation |
| Ezetimibe | Ezetimibe | ↓ LDL | Add-on to statins or statin-intolerant | GI upset, rare liver effects |
| PCSK9 Inhibitors | Evolocumab, Alirocumab | ↓↓↓ LDL | High-risk, familial hypercholesterolemia | Injection site reactions |
| Bempedoic Acid | Bempedoic acid | ↓ LDL | Statin-intolerant patients | Hyperuricemia, tendon rupture |
| Fibrates | Fenofibrate, Gemfibrozil | ↓ TG, ↑ HDL | Severe hypertriglyceridemia | Myopathy (esp. with statins), GI upset |
| Omega-3 Fatty Acids | Icosapent ethyl (Rx fish oil) | ↓ TG | High triglycerides, CV risk reduction | GI upset, bleeding risk |
| Niacin | Niacin | ↓ LDL, ↓ TG, ↑ HDL | Rarely used now due to side effects | Flushing, liver toxicity |
Statins:
Mechanism of Action:
-
Inhibit Hydroxy Methyl Glutaryl -CoA reductase → ↓ cholesterol synthesis in liver
-
Liver compensates by ↑ LDL receptor expression → ↑ LDL clearance from blood
-
Result: ↓ LDL (primary), modest ↓ TG, slight ↑ HDL
-
Side Effects & Management:
- Muscle pain/myopathy → check CK, reduce dose, switch statin, or try alternate-day dosing.
- rhabdomyolysis (rare) → stop statin, hospitalize, hydrate.
- Elevated liver enzymes → monitor AST/ALT, stop or reduce dose if > 3 × ULN.
- GI upset → take with food ,at night
- Drug interactions
STATIN INTENSITY
High-Intensity (↓ LDL ≥50%)
- Atorvastatin 40–80 mg
- Rosuvastatin 20–40 mg
Moderate-Intensity (↓ LDL 30–49%)
- Atorvastatin 10–20 mg
- Rosuvastatin 5–10 mg
- Simvastatin 20–40 mg
Management according to ACC/AHA
Initial Evaluation (All Patients)
A. Fasting or Non-fasting Lipid Panel
- Total cholesterol
- LDL-C
- HDL-C
- Triglycerides
B. Identify Secondary Causes,. Review Medications
C. Assess ASCVD Risk
- Use Pooled Cohort Equations (age 40–75)
- 10-year ASCVD risk categories:
- Low: <5%
- Borderline: 5–7.4%
- Intermediate: 7.5–19.9%
- High: ≥20%
Lifestyle Measures(All Patients)
- Heart-healthy diet (Mediterranean/DASH; Dietary Approaches to Stop Hypertension )
- Weight reduction
- Physical activity (≥ 150 min/week)
- Smoking cessation
- Limit alcohol
STATIN BENEFIT GROUPS (ACC/AHA)
Statins recommended for 4 major groups
- Clinical ASCVD
- LDL ≥ 190 mg/dL
- Diabetes (age 40–75)
- High ASCVD risk (≥7.5%)
Clinical ASCVD
Includes:
- Prior MI, stroke/TIA
- PAD
- Coronary or arterial revascularization
Management
- High-intensity statin
- Atorvastatin 40–80 mg
- Rosuvastatin 20–40 mg
Goal
- ≥ 50% LDL-C reduction
- LDL-C < 70 mg/dL (practical target)
If LDL ≥ 70 despite max statin
- Add ezetimibe
- If still ≥ 70 → PCSK9 inhibitor
Severe Hypercholesterolemia
LDL-C ≥ 190 mg/dL (age 20–75)
Management
- High-intensity statin (no risk calculation needed)
If LDL ≥ 100
- Add ezetimibe
- Consider PCSK9 inhibitor (esp. familial hypercholesterolemia)
Diabetes Mellitus (Age 40–75, LDL ≥70)
Management
- Moderate-intensity statin (minimum)
- High-intensity statin if:
- Age 50–75
- Multiple ASCVD risk factors
Primary Prevention (No ASCVD, No DM, LDL 70–189)
Based on 10-yr ASCVD Risk
- Borderline (5–7.4%):
- → Consider statin if risk enhancers present
- Intermediate (7.5–19.9%):
- → Moderate-intensity statin
- High (≥ 20%):
- → High-intensity statin
. Risk-Enhancing Factors (Help Decide Statin Use)
- Family history of premature ASCVD
- LDL ≥ 160 mg/dL
- Metabolic syndrome
- CKD
- Chronic inflammatory diseases
- South Asian ethnicity
- Elevated TG ≥ 175 mg/dL
- hs-CRP ≥ 2 mg/L
- Lp(a), ApoB elevation
Hypertriglyceridemia
- TG <5.6 mmol/L (150–499 mg/dL)
- Statins first-line for ASCVD risk reduction
- Consider icosapent ethyl (EPA) in high-risk patients on statins
- Fibrates not routine
- TG ≥5.6 mmol/L (≥500 mg/dL)
- Goal: prevent pancreatitis
- Fibrate first-line
- Add omega-3 fatty acids
- Statin if ASCVD risk present
- TG ≥11.3 mmol/L (≥1000 mg/dL)
- Very high pancreatitis risk
- Very low-fat diet, strict glucose control
- Hospitalize if symptomatic
General Management Flowchart

ACC/AHA-Based Statin Decision

Hypertriglyceridemia Management
Triglycerides Level
<150 mg/dL → Normal
150–499 mg/dL → Lifestyle + Statin (if ASCVD risk)
≥500 mg/dL → Fibrate ± Omega-3
Prevent Acute Pancreatitis
For all patients: assess secondary causes, recommend a heart-healthy diet, exercise ≥150 minutes/week, support weight management and smoking cessation. Recheck lipids 4–12 weeks after starting or changing statin therapy; reassess severe hypertriglyceridemia sooner as clinically needed. All medication doses are oral unless otherwise stated.
Scenario 1
Patient: 62-year-old male, history of MI 2 years ago
Lipid profile:
- Total cholesterol: 220 mg/dL ↑ — borderline high
- LDL-C: 150 mg/dL ↑ — borderline high; above secondary-prevention goal
- HDL-C: 35 mg/dL ↓ — low
- TG: 150 mg/dL ↑ — borderline high
Risk group: Established ASCVD — secondary prevention; statin indicated regardless of calculated risk.
Diagnosis: Established ASCVD (previous MI) with elevated LDL; secondary prevention.
Treatment:
- High-intensity statin: atorvastatin 40–80 mg/day or rosuvastatin 20–40 mg/day.
- Goal: ≥50% LDL reduction and LDL <70 mg/dL.
- If LDL remains ≥70 on the maximum tolerated statin, add ezetimibe 10 mg/day; consider a PCSK9 inhibitor if still above goal.
Scenario 2
Patient: 35-year-old female, no ASCVD, family history of premature CAD
Lipid profile:
- Total cholesterol: 330 mg/dL ↑ — high
- LDL-C: 250 mg/dL ↑ — very high (≥190)
- HDL-C: 40 mg/dL ↓ — low for a woman
- TG: 150 mg/dL ↑ — borderline high
Risk group: Severe hypercholesterolemia / suspected familial hypercholesterolemia — high lifetime ASCVD risk; statin indicated without risk calculation.
Diagnosis: Severe hypercholesterolemia; suspected heterozygous familial hypercholesterolemia because of LDL 250 mg/dL and premature CAD in the family.
Treatment:
- High-intensity statin, without calculating 10-year ASCVD risk.
- Add ezetimibe 10 mg/day if LDL remains ≥100 mg/dL on the maximum tolerated statin; consider a PCSK9 inhibitor if inadequately controlled.
- Exclude secondary causes, arrange lipid-specialist assessment and screen first-degree relatives.
- Discuss pregnancy plans and review lipid-lowering medications before conception.
Scenario 3
Patient: 50-year-old male, type 2 diabetes, no ASCVD
Lipid profile:
- Total cholesterol: 210 mg/dL ↑ — borderline high
- LDL-C: 130 mg/dL ↑ — borderline high
- HDL-C: 38 mg/dL ↓ — low
- TG: 180 mg/dL ↑ — borderline high
Risk group: Diabetes, age 40–75 — primary prevention; statin-benefit group.
Diagnosis: Diabetic mixed dyslipidemia: elevated LDL, mildly elevated TG and low HDL.
Treatment:
- At least a moderate-intensity statin; high-intensity therapy is reasonable given age 50 and additional lipid risk factors, e.g. atorvastatin 40 mg/day.
- Optimize glucose control, physical activity and weight.
- No routine fibrate for TG 180 mg/dL; do not prescribe medication solely to raise HDL.
Scenario 4
Patient: 45-year-old female, no ASCVD, non-diabetic, borderline 10-year ASCVD risk 7%
Lipid profile:
- Total cholesterol: 210 mg/dL ↑ — borderline high
- LDL-C: 140 mg/dL ↑ — borderline high
- HDL-C: 50 mg/dL ↔ — acceptable; lower threshold for women
- TG: 150 mg/dL ↑ — borderline high
Risk group: Borderline 10-year ASCVD risk (7%), primary prevention indicated.
Diagnosis: Elevated LDL with borderline primary-prevention ASCVD risk
Treatment:
- Lifestyle treatment first.
- Consider a moderate-intensity statin, e.g. atorvastatin 10–20 mg/day, if risk enhancers are present, such as premature family ASCVD, CKD or chronic inflammatory disease.
- Consider coronary artery calcium scoring if the statin decision remains uncertain.
Scenario 5
Patient: 40-year-old male, presents for routine check-up,
BMI 32
Lipid profile:
- Total cholesterol: 250 mg/dL ↑ — high
- LDL-C: 120 mg/dL ↑ — above optimal if valid; conventional calculated LDL is unreliable at TG 800
- HDL-C: 35 mg/dL ↓ — low
- TG: 800 mg/dL ↑ — severe hypertriglyceridemia
Risk group: Increased pancreatitis risk; ASCVD risk requires further assessment.
Diagnosis: Severe hypertriglyceridemia with obesity and increased pancreatitis risk. The available information does not establish a specific inherited disorder or metabolic syndrome.
Treatment:
- Confirm fasting lipids and assess secondary causes, especially diabetes, hypothyroidism, alcohol and medications.
- Low-fat diet, no alcohol, reduce refined carbohydrates and pursue weight loss.
- Fenofibrate, with dosing guided by kidney function; prescription omega-3 fatty acids may be an alternative or add-on. Initial goal: TG <500 mg/dL.
- Assess ASCVD risk to determine whether a statin is also indicated; prefer fenofibrate over gemfibrozil if combined with a statin.
- Severe abdominal pain or vomiting requires urgent assessment for pancreatitis.
Summary
- Dyslipidemia is a major, modifiable cause of ASCVD
- LDL-C is the primary treatment target
- Statins are first-line therapy
- Lifestyle modification is essential for everyone
- Risk stratification guides therapy
- Add non-statins when needed
- Triglycerides matter /pancreatitis risk
- Treat secondary causes first