Systemic Sclerosis (Scleroderma)
By Isra
Definition
- Systemic sclerosis is a chronic autoimmune connective tissue disease characterized by:
- Fibrosis of skin and internal organs.
- Vasculopathy (obliterative small-vessel disease).
- Immune dysregulation with autoantibody production.
Note: ‘Sclero’ = hard, ‘derma’ = skin, but disease is systemic, not only cutaneous.
Epidemiology
- Prevalence: 50–300 per million (rare disease).
- Gender: Female : Male 4–6 : 1.
- Age: Onset typically 30–50 years.
- Ethnic variation: African ancestry more severe, diffuse disease, worse outcomes. Caucasians more limited disease.
- Genetics: HLA associations (e.g. DRB11104, DQA10501).
Pathophysiology (Stepwise)
- Trigger + Genetic susceptibility → environmental exposures (silica, solvents) in a predisposed person.
- Vascular injury → endothelial apoptosis, intimal proliferation, narrowing/obliteration → Raynaud’s, digital ulcers.
- Immune activation → T cells, B cells, cytokines (IL-4, IL-6, TGF- ), autoantibodies (anti-centromere, anti-Scl-70, anti-RNA pol III).
- Fibroblast activation → overproduction of collagen.
- End-organ fibrosis → skin thickening, lung fibrosis, renal crisis, cardiac fibrosis, GI dysmotility.
Classification (EULAR/ACR 2013)
A. Localized forms (not systemic):
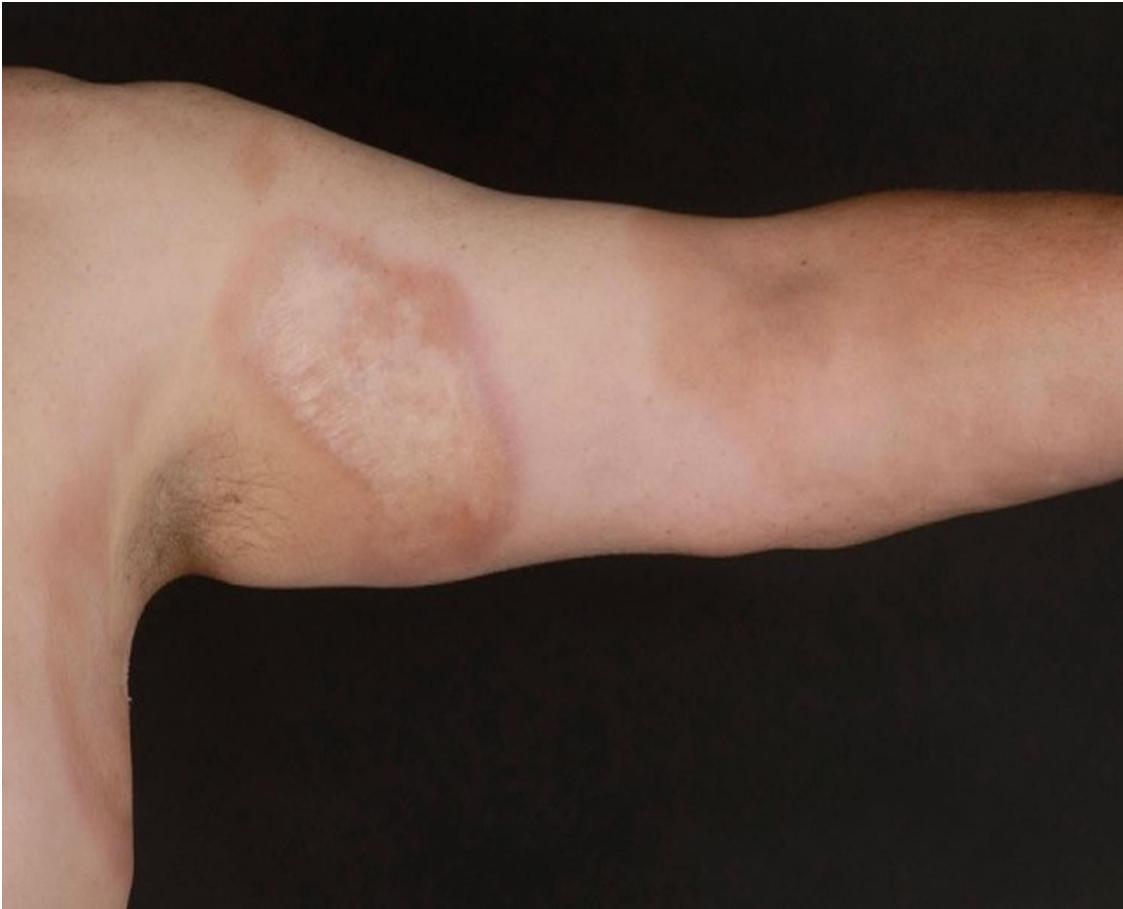
- Morphea: patchy areas of skin thickening, only skin/subcutaneous tissue.
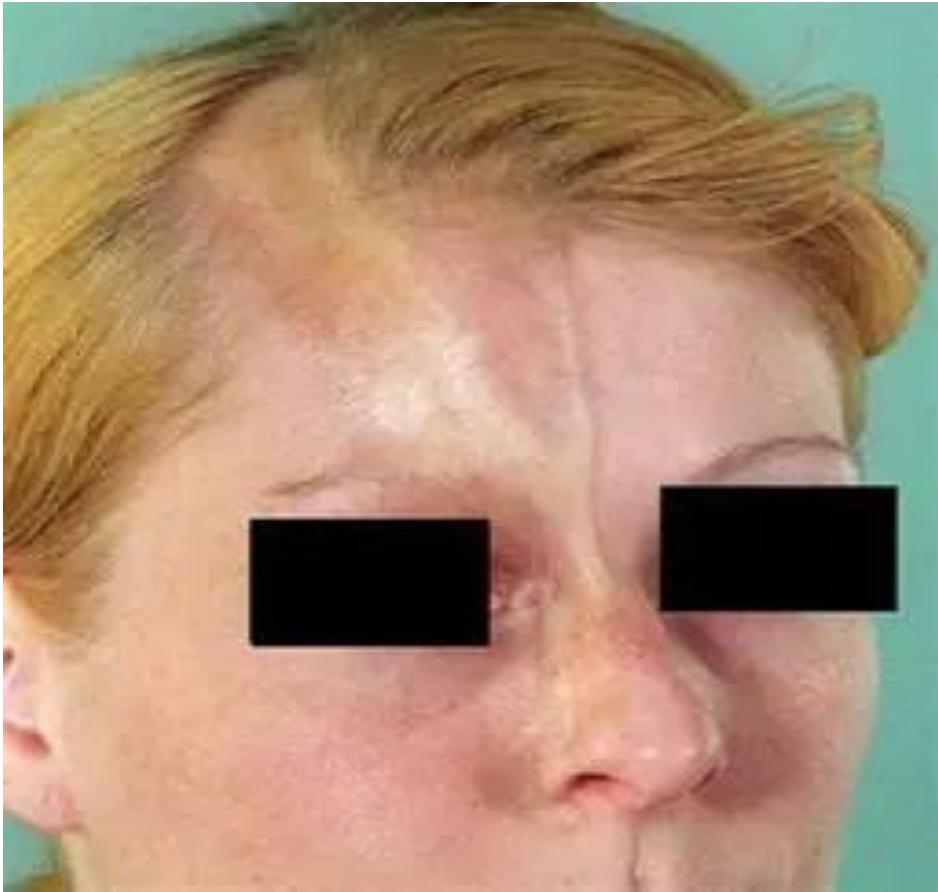
- Linear scleroderma: streak of thickened skin, may involve muscle/bone.
These forms do NOT involve internal organs.
B. Systemic sclerosis (two major subsets):
- Limited cutaneous systemic sclerosis (lcSSc / CREST)
- Diffuse cutaneous systemic sclerosis (dcSSc)
Limited cutaneous systemic sclerosis (lcSSc / CREST)
- Skin thickening limited to face, hands, distal forearms/legs.
- CREST: Calcinosis, Raynaud’s phenomenon, Esophageal dysmotility, Sclerodactyly, Telangiectasia.
- Organ features: Pulmonary arterial hypertension (PAH), GI reflux, dysmotility.
- Antibody: Anti-centromere.
- Course: Slow, indolent.
The limited symptoms of scleroderma are referred to as CREST
Calcinosis - Calcium deposits in the skin.
Raynaud’s phenomenon - spasms of blood vessels in response to cold or stress.

Esophageal dysfunction - acid reflux and decrease in motility of esophagus.
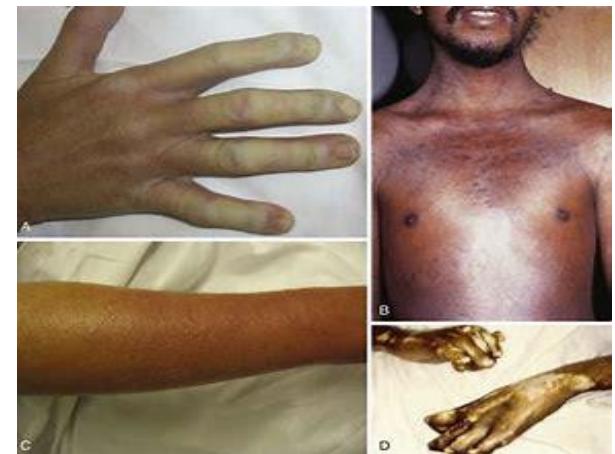
Sclerodactyly - thickening and tightening of the skin on the fingers and hands.

Telangiectasias - dilation of capillaries causing red marks on surface of the skin.

Diffuse cutaneous systemic sclerosis (dcSSc)
- Skin thickening extends proximally (upper arms, thighs, trunk).
- Rapid progression.
- Organ features: Interstitial lung disease (fibrosis), Renal crisis (malignant HTN, AKI, MAHA), Cardiac involvement.
- Antibodies: Anti-Scl-70 (topoisomerase I), Anti-RNA polymerase III.
- Course: Aggressive, early visceral disease.
Clinical Manifestations (by system)
- Skin: Tight shiny skin, sclerodactyly, digital ulcers, calcinosis.
- Vascular: Raynaud’s phenomenon, telangiectasia, PAH.
- GI tract: Reflux, dysphagia, small bowel dysmotility, malabsorption.
- Lungs: Interstitial lung disease (diffuse), Pulmonary hypertension (limited).
- Renal: Scleroderma renal crisis, MAHA (diffuse).
- Cardiac: Restrictive cardiomyopathy, arrhythmias, pericardial effusion.
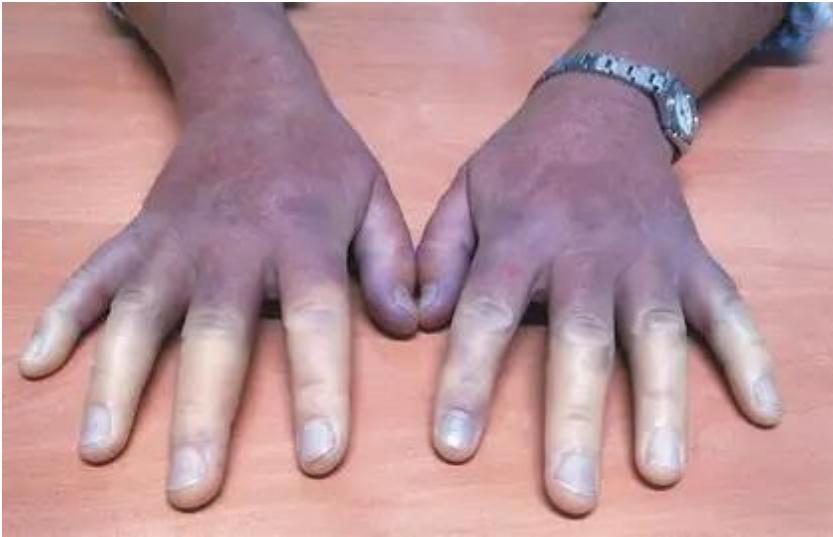
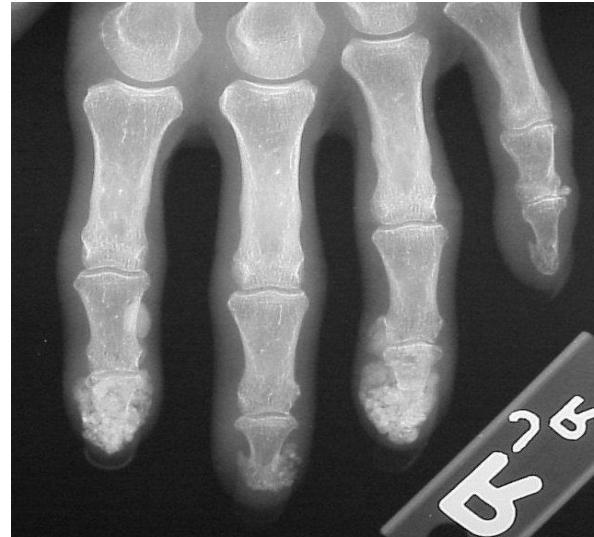
R 6
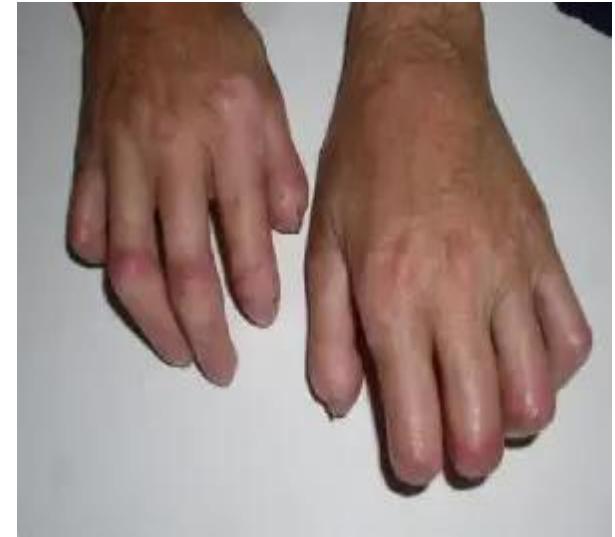

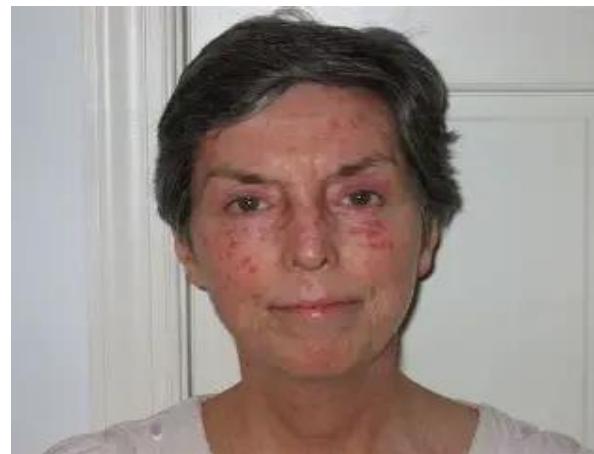
Investigations
- Autoantibodies: ANA (>90%), Anti-centromere (limited), Anti-Scl-70 (diffuse, ILD), Anti-RNA polymerase III (renal crisis).
- Nailfold capillaroscopy: capillary dropout, dilatation.
- HRCT chest: interstitial lung disease.
- Echocardiography / RHC: pulmonary hypertension.
- Renal function and BP monitoring.
Management
- General: Avoid cold, stop smoking, vaccinate (influenza, pneumococcus).
- Vascular / Raynaud’s: Calcium channel blockers, PDE-5 inhibitors, prostacyclin analogs, bosentan.
- Fibrosis / Skin: Methotrexate, mycophenolate, cyclophosphamide; stem cell transplant in severe diffuse cases.
- Lungs: ILD → mycophenolate, cyclophosphamide, nintedanib; PAH → sildenafil, bosentan, epoprostenol.
- Renal crisis: ACE inhibitors (captopril), avoid high-dose steroids.
- GI: PPIs for reflux, prokinetics, antibiotics for bacterial overgrowth.
Cancers Associated with Systemic Sclerosis
- Lung Cancer: Most strongly associated. Risk highest in patients with interstitial lung disease (ILD) and long-standing pulmonary fibrosis. Smoking further increases risk.
- Breast Cancer: Increased incidence, especially in women with diffuse cutaneous SSc. Sometimes appears within a few years of onset.
- Esophageal Carcinoma: Due to long-standing esophageal dysmotility and reflux (GERD).
- Hematological Malignancies: Non-Hodgkin lymphoma.
- Other Solid Tumors (less frequent): Liver cancer, Bladder cancer.
Antibody Associations & Cancer Risk
- Anti-RNA polymerase III antibodies → strongest link with cancer (breast, lung). Often cancers diagnosed within 2–3 years of SSc onset.
- Anti-Scl-70 (topoisomerase I) → linked with ILD, hence indirect lung cancer risk.
- Anti-centromere antibodies → lower cancer association.
Notes
- Scleroderma = vascular disease + immune dysregulation + fibrosis.
- Limited (CREST): slow, distal, pulmonary hypertension.
- Diffuse: rapid, proximal, ILD + renal crisis.
- Localized (morphea/linear): skin only.
- Prognosis depends on lungs, kidneys, heart involvement.
- There is no consistent disease-specific antibody for localized forms.
- Always consider associated malignancies screening.
GOOD LUCK