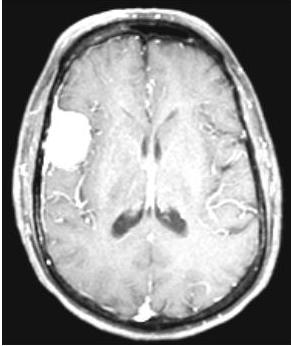
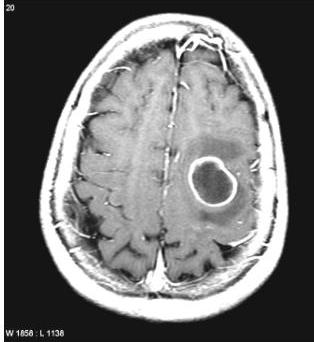
Brain Tumor
Dr.Safdar Malik MD FCPS
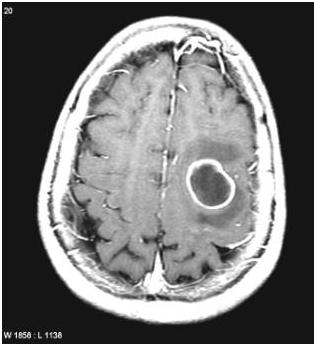
Background
- The incidence of CNS tumors ≈ 1% of all cancers.
- Third leading cause of cancer deaths in people 15 to 34 years of age.
- Second leading cause of cancer deaths in children.
Risk Factors
- Radiation therapy.
- can cause
- and can change grading of tumors
- neurofibromatosis type 1 and 2
- Genetics; e.g: NF, Tuberous sclerosis, Von Hippel-Lindau synd., Li-Fraumeni syndrome, and Turcot syndrome.
- Lymphomas that begin in the brain.
- Male gender (except meningioma, more in females).
Key
- Intra Axial the tumor arise from Center eg: Brain Cells tumor < Astrosite - astrocytoma glial cells
- Extra Axial arise from meninges
- Tumors In Adult
- Tumors In Children
Origin
- Glial Tissue from brain cells (Glioma, Astrocytoma)
- MENENGIES meningioma not very common
- Ependymal Layer Cells which cover Ventricles
- Choroid plexus Production of CSF it’s in all brain except (Lateral Ventricle) ⇒ Papilloma
- Bone
- PNET
- Glands Brain glands < pituitary adenoma
- Others
Location
-
In Pediatric most of tumors is in posterior fossa
-
In adult more in supratentorial
-
Supra Tentorial
-
Infra Tentorial
-
Intra Axial
-
Extra Axial
-
Sellar & Supra Sellar
-
Pineal region
-
Intra Ventricular
-
Cp angle
The brain metastasis locally specically meniggemia can involve skull bone not to other organs
WHO Classification & Grading of CNS Tumours
Brain has no lymph nodes so no mel’s in Brain → we don’t use TAM staging system
| I | II | III | IV | Is there’s only one metastasis called DGP met, I | II | III | IV | |
|---|---|---|---|---|---|---|---|---|
| Astrocytic tumours | ||||||||
| Subependymal giant cell astrocytoma | benign↓ | highly graded | Central neurocytoma | • | ||||
| Pilocytic astrocytoma | we can remove it | • | completely and no need | Dr. Balshaway | Extraventricular neurocytoma | • | ||
| Pilomyxoid astrocytoma | • | Cerebellar liponeurocytoma | • | |||||
| Diffuse astrocytoma | • | Paraganglioma of the spinal cord | • | |||||
| Pleomorphic xanthoastrocytoma | • | Papillary glioneuronal tumour | • | |||||
| Anaplastic astrocytoma | • | Rosette-forming glioneuronal tumour of the fourth ventricle | • | |||||
| Glioblastoma always in Adult | • | Pineal tumours | ||||||
| Giant cell glioblastoma | • | Pineocytoma | • | |||||
| Gliosarcoma | • | Pineal parenchymal tumour of intermediate differentiation | • | • | ||||
| Oligodendroglial tumours | Pineoblastoma in Pediatric | • | ||||||
| Oligodendroglioma | • | Papillary tumour of the pineal region | • | • | ||||
| Anaplastic oligodendroglioma | • | Embryonal tumours | ||||||
| Oligoastrocytic tumours | Medulloblastoma | • | ||||||
| Oligoastrocytoma | • | CNS primitive neuroectodermal tumour (PNET) | • | |||||
| Anaplastic oligoastrocytoma | • | Atypical teratoid / rhabdoid tumour | • | |||||
| Ependymal tumours | Tumours of the cranial and paraspinal nerves | |||||||
| Subependymoma | • | Schwannoma | • | |||||
| Myxopapillary ependymoma | • | Neurofibroma | • | |||||
| Ependymoma | • | Perineurioma | • | • | • | |||
| Anaplastic ependymoma | • | Malignant peripheral nerve sheath tumour (MPNST) | • | • | ||||
| Choroid plexus tumours | Meningeal tumours | |||||||
| Choroid plexus papilloma | • | Meningioma | • | |||||
| Atypical choroid plexus papilloma | • | Atypical meningioma | • | |||||
| Choroid plexus carcinoma | • | Anaplastic / malignant meningioma | • | |||||
| Other neuroepithelial tumours | Haemangiopericytoma | • | ||||||
| Angiocentric glioma | • | Anaplastic haemangiopericytoma | • | |||||
| Chordoid glioma of the third ventricle | • | Haemangioblastoma | • | |||||
| Neuronal and mixed neuronal-glial tumours | Tumours of the sellar region | |||||||
| Gangliocytoma | • | Craniopharyngioma | • | |||||
| Ganglioglioma | • | Granular cell tumour of the neurohypophysis | • | |||||
| Anaplastic ganglioglioma | • | Pituicytoma | • | |||||
| Desmoplastic infantile astrocytoma and ganglioglioma | • | Spindle cell oncocytoma of the adenohypophysis | • | |||||
| Hyperobscoplastic neuroepithelial tumour | • | 7 |
CBTRUS Statistical Report
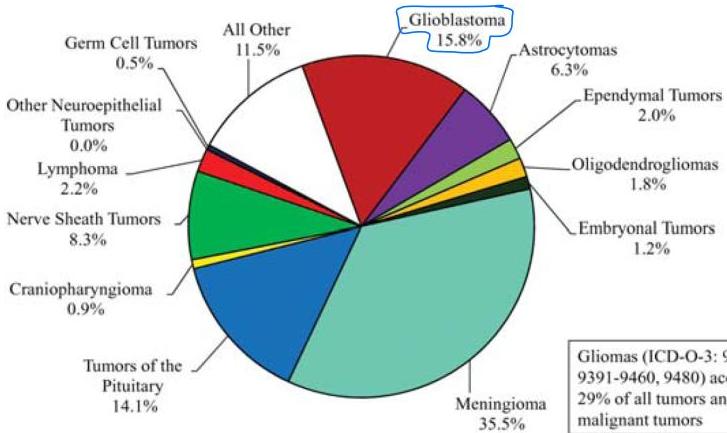
Gliomas account for 29% of all tumors and 80% of malignant tumors
Common Primary Neoplasms
Common 1° neoplasms:
- Gliomas #1 (50%)
- Meningiomas #2 (25%)
Among children:
80-90% IN POSTERIOR FOSSA
- Astrocytomas benign
- Medulloblastoma
- Ependymoma
Signs & Symptoms
Symptoms & Signs Due to Raised ICP
- Recurring, persistent, deep, dull headaches.
- Vomiting.
- Dizziness.
- Seizures.
- Papilledema.
- Bradycardia.
- Hypertension.
Symptoms Due to Origin of Tumor
-
SYMPTOMS DUE TO ORIGION OF TUMOR
-
Seizures
- epilipsy for first time do CT scan
-
Weakness or paralysis, part of the body.
-
Changes in sensory perceptions, such as vision, hearing, touch, taste and smell.
-
Changes in personality and/or thought processes.
-
Cerebellar .
-
Pituitary hormonal imbalance
Functions of the Cerebral Lobes
Different lobes of the cerebrum carry out specific tasks.
- The frontal lobe is generally where “higher functions” of thought, memory, judgment and movement originate.
- The parietal lobe processes sensory information and is involved in orientation and recognition.
- The occipital lobe processes visual information.
- The temporal lobe is involved in hearing, language, expression and memory.
Glioma
Characteristics
- Poorly defined
- Highly agressive in adult
- Occurs in the white matter of cerebral hémisphères so can occure any site of brain.
- Spread extremely rapidly
Average Age of Onset
- Fifth decade
General Name for Several Tumors that Arise from Glial Cells
- Astrocytes (Glioblastoma multiforme is the most common)
- Ependymal
- Oligodendrocytes
Symptoms Between the Hemispheres
- Between the hemispheres:
- ✓ Seizures, lower extremity weakness, headache, personality changes, dementia, increasing apathy, flattening of affect, unsteadiness, tremor
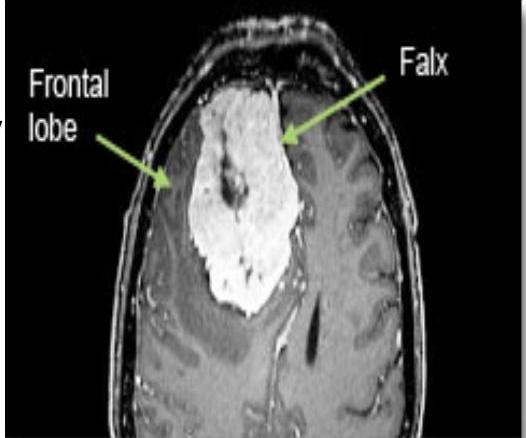
Intra-Axial Imaging
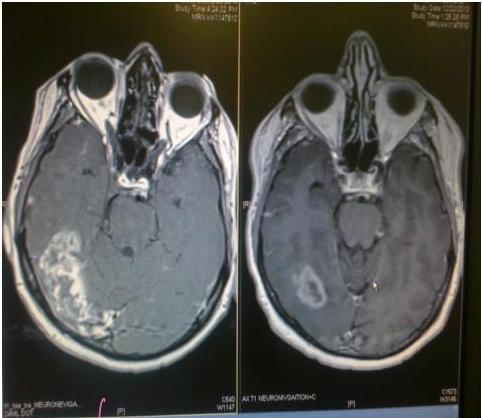
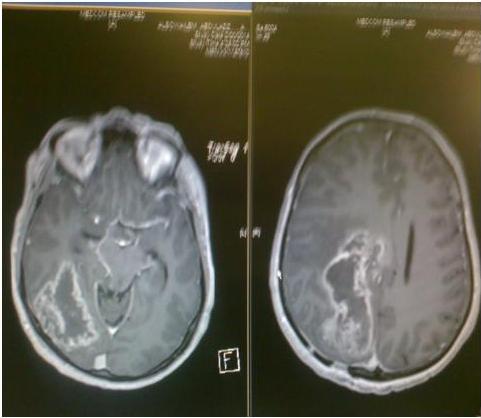
intra-axial
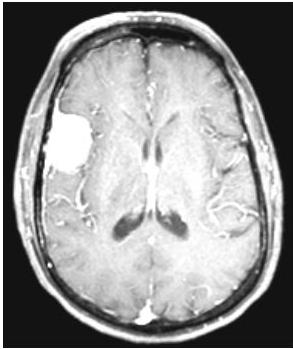
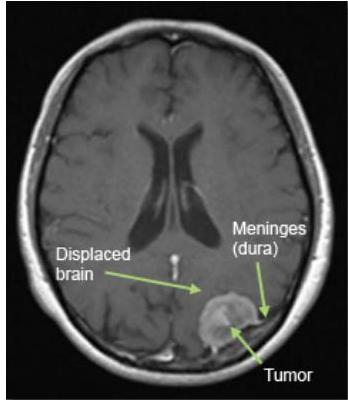
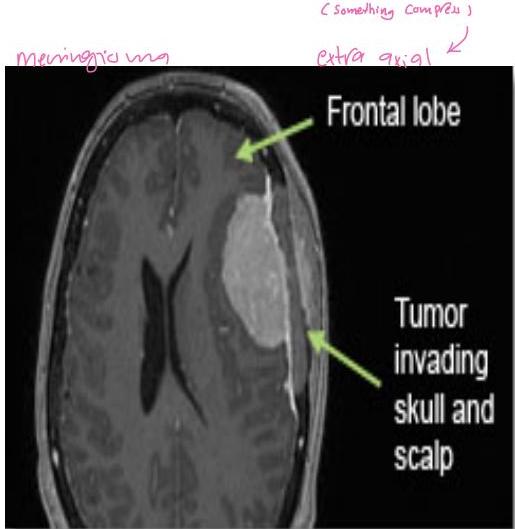
Meningioma (Extra-Axial)
Characteristics
Tumors that arise from meninges: arachnoid
- grow on the surface of the brain (or spinal cord), and therefore push the brain away
- Most are considered “benign”
- slow-growing
- low potential to spread
meningioma (Extra - acid)
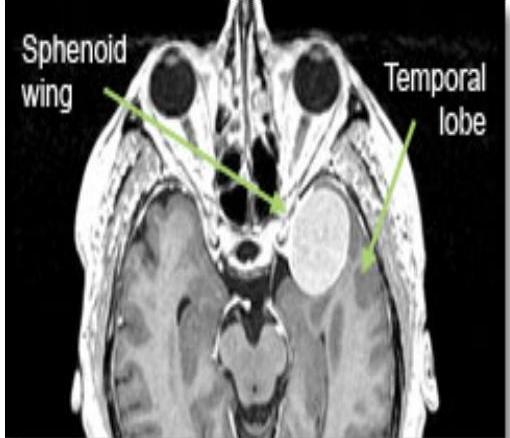
Sphenoid Wing
Sphenoid Wing :
- Eye-bulging
- decreased vision
- paralysis of eye movement
- seizures
- memory difficulty
- personality change
- headache
Symptoms According to Location: Surface of the Brain
Symptoms according to location:
- Seizures
- headache
- extremity weakness
- difficulty speaking
- visual field deficit
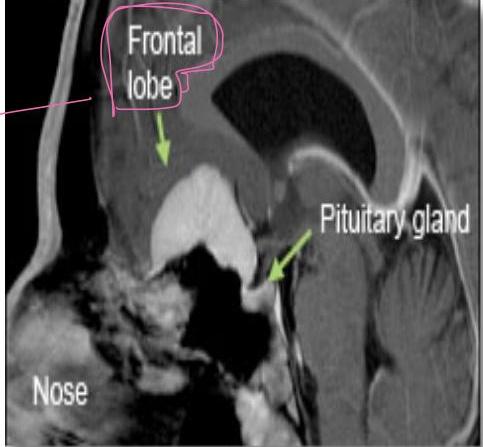
Olfactory Groove and Sella
Olfactory Groove and sella :
- Anosmia
- subtle personality changes
- mild difficulty with memory
- euphoria
- diminished concentration
- urinary incontinence
- visual impairment
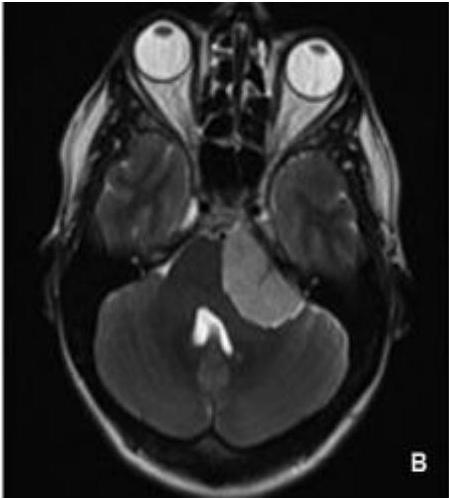
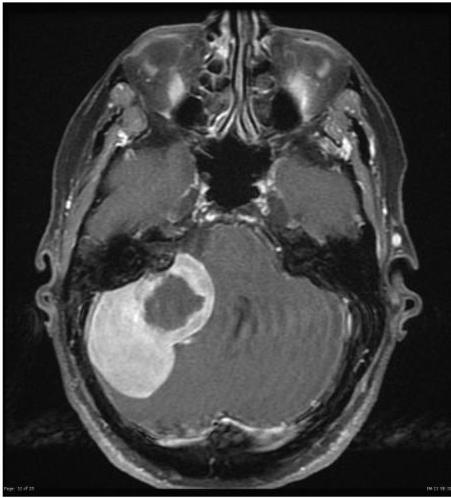
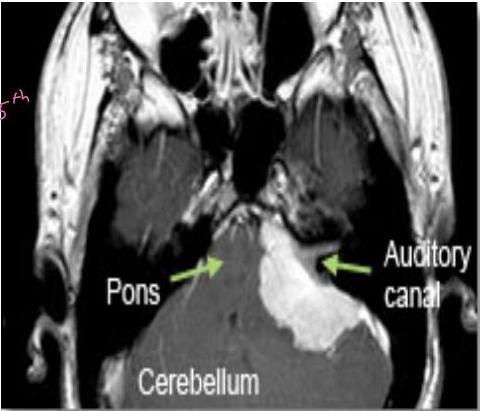
CP Angle (Cerebellopontine Angle)
Tumour Types — All Benign
- Schawanoma 8th cr nerve, 5th cr nerve and sometimes 7th vestibuloculture
- Meningioma
- Arachnoid Cyst
- Haemangioblastoma
Imaging
Cerebellopontine Angle: Symptoms
Cerebellopontine angle:
- Loss of hearing, = 8th
- Facial muscle weakness, = 7th, 8th
- dizziness, unsteadiness, incoordination, hydrocephalus, voice and swallowing difficulties.
Pituitary Tumors
-
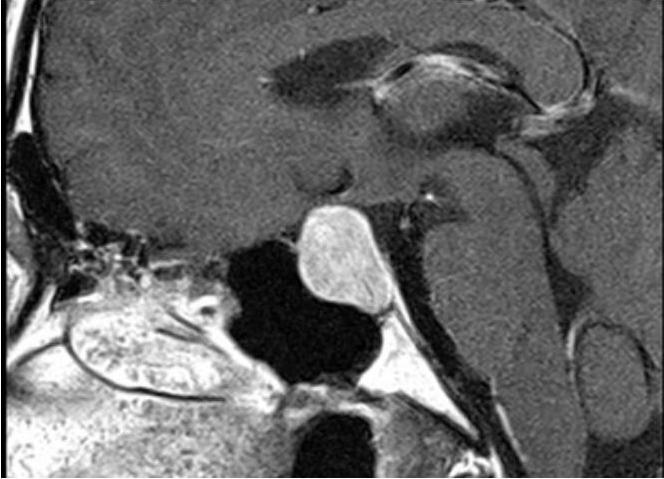
→ when it increase in size it press on optic chiasma so pit can’t see temporal side
-
→ has 2 types: Hypersecretion of hormone, remove tumor by Nasal-endoscopic resection
-
Hypersecretion of hormone: symptom depend on which hormone
-
Pituitary Adenomas
-
Pituitary Carcinomas
-
Sarcomas
-
Meningioma
-
Chardomas
-
Haemangiblastoma
-
Cyst
-
Rathkes Cleft cyst, Arachnoid cyst & Mucoceles. Dermoid & Epidermoid
-
Craniopharangioma.
-
Astrocytoma.
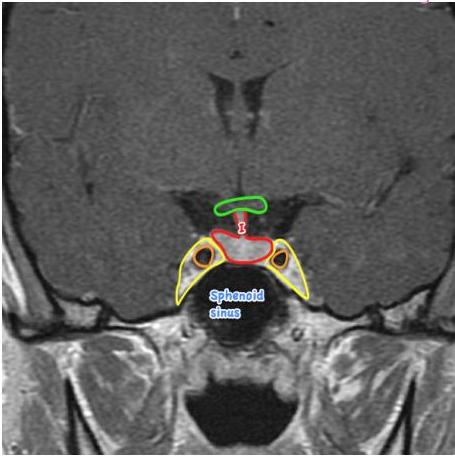
Imaging
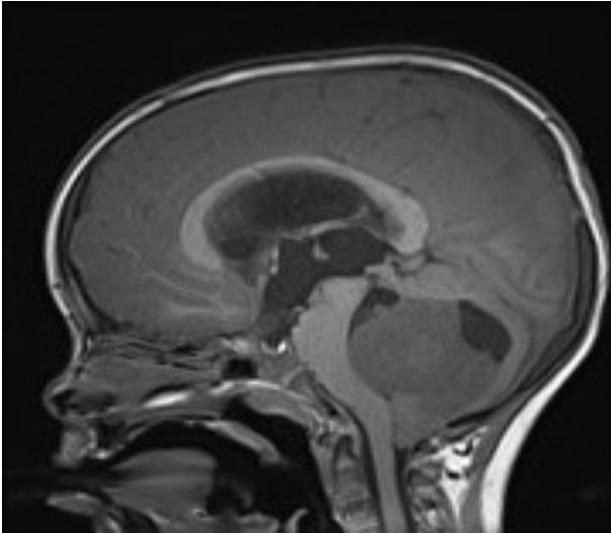
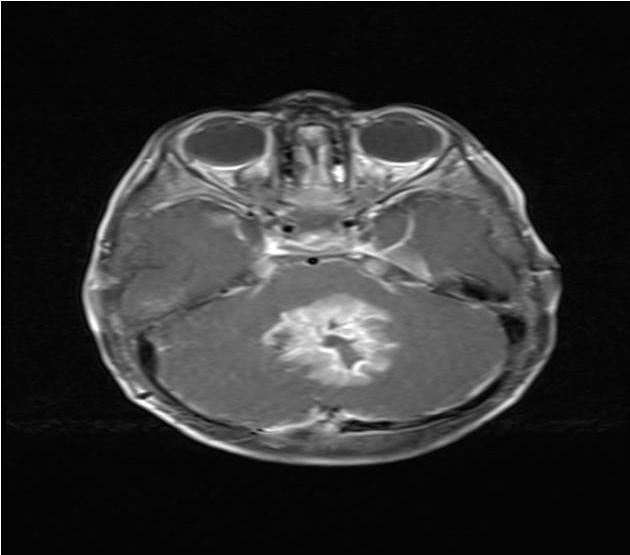
Post Fossa Sol
- DUE TO ↑ ICP
- HYDROCEPHALOUS because of obstruction
- ATAXIA/IMBALANCE
- CEREBELLER SIGNS
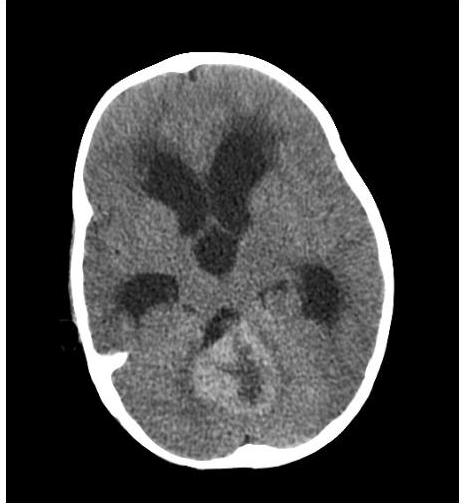
PFT
Diagnosis & Treatment Planning
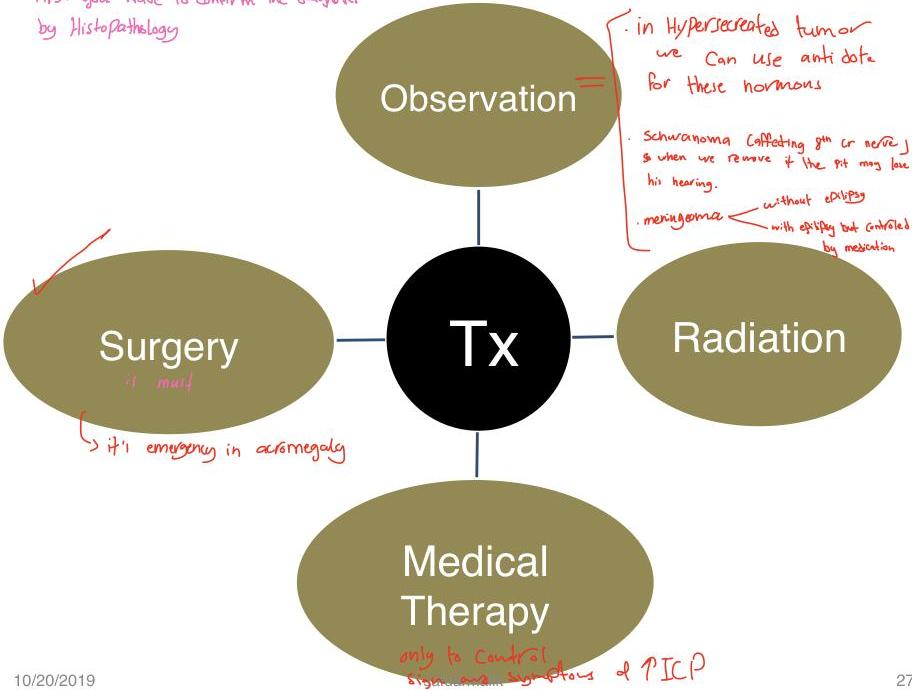
Confirm the Diagnosis by Histopathology
First you have to confirm the diagnosis by Histopathology
Factors Influencing the Treatment Plan
- Location of tumor.
- Radiological appearance of tumor.
- Size of tumour
- The risks and potential benefits of available treatment options
- General health & comorbidities.
- Age
- The type of healthcare services available / your ability to travel
Options
The most common treatment are:
- Surgery
- Drug therapy (chemotherapy, immunotherapy, gene therapy) steroid
- Radiotherapy
- Combined chemo/radiotherapy
- Best supportive care
- Watch and wait
Radical vs Palliative Intent
- Radical: In some cancers the intent is to cure. For brain tumours the aim is to stabilize the disease with best standard treatment which currently is a combination of radiotherapy and oral chemotherapy.
- Palliative: The intent here is to relieve the symptoms when a cure is not possible. Sometimes it is better to look after the symptoms because to deal with the cause may be too damaging.
Scenario
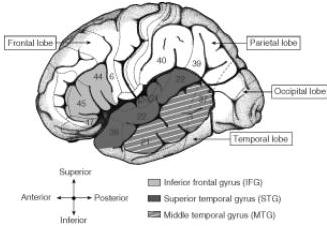
Broca’s area located around pars opercularis (44) and pars triangularis (45)
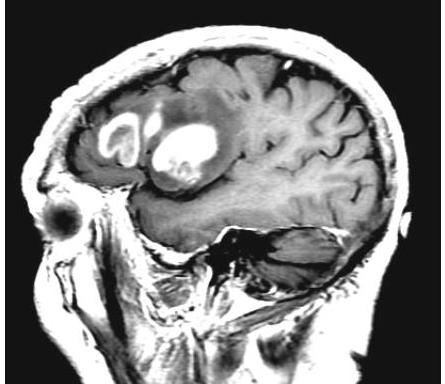
affect the sperm area
Gliomas
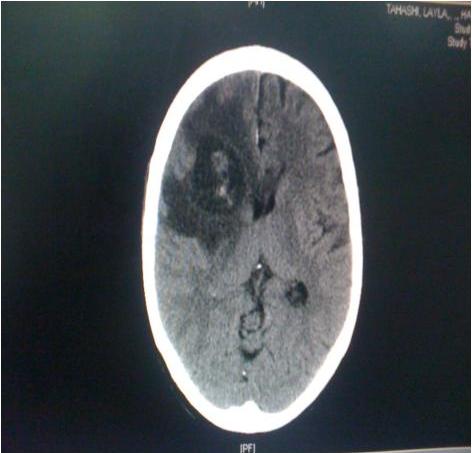
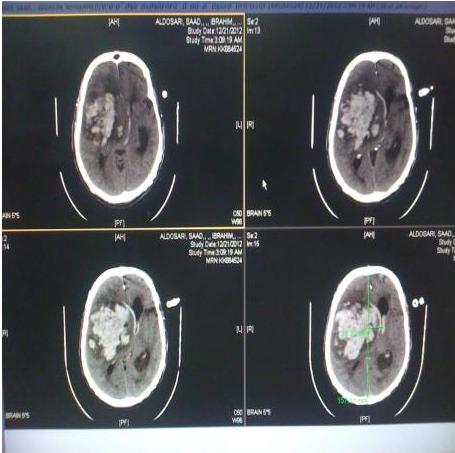
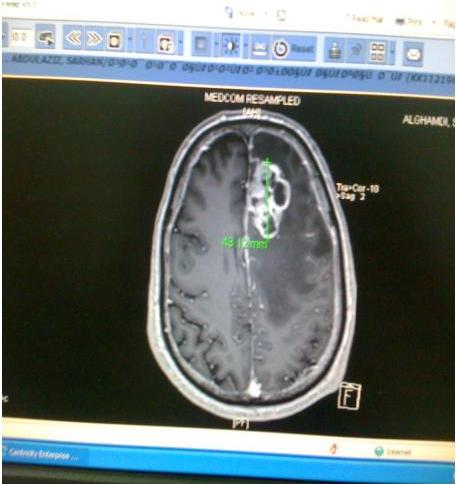
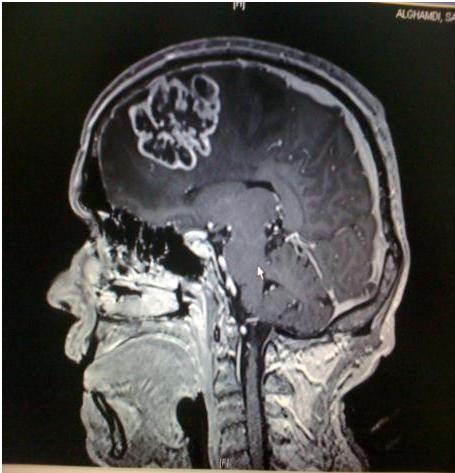
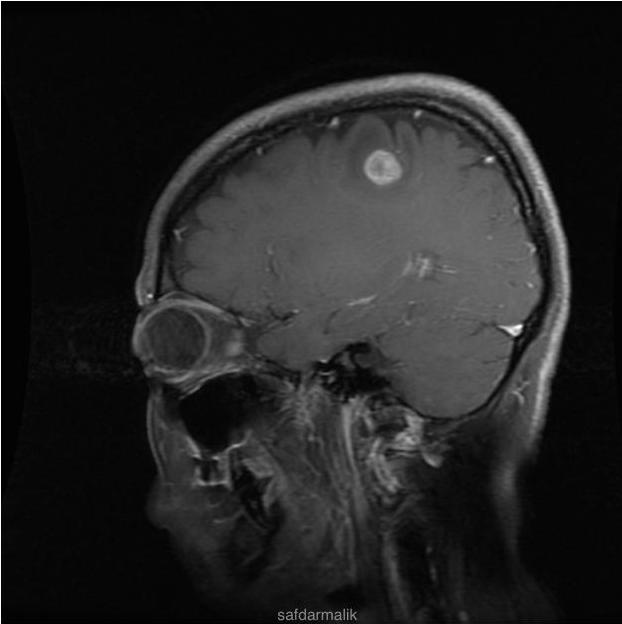
Differential Diagnosis: Meningioma vs Metastasis vs Glioma
Not the same!
- Meningioma
- Metastasis
- Glioma