SURGERY 2
The Dangerous Miss: Recognizing Acute Mesenteric Ischemia
not easy to diagnose
80% of acute mesenteric ischemia cases result in mortality because of missed diagnosis. Here’s how to recognize the signs.
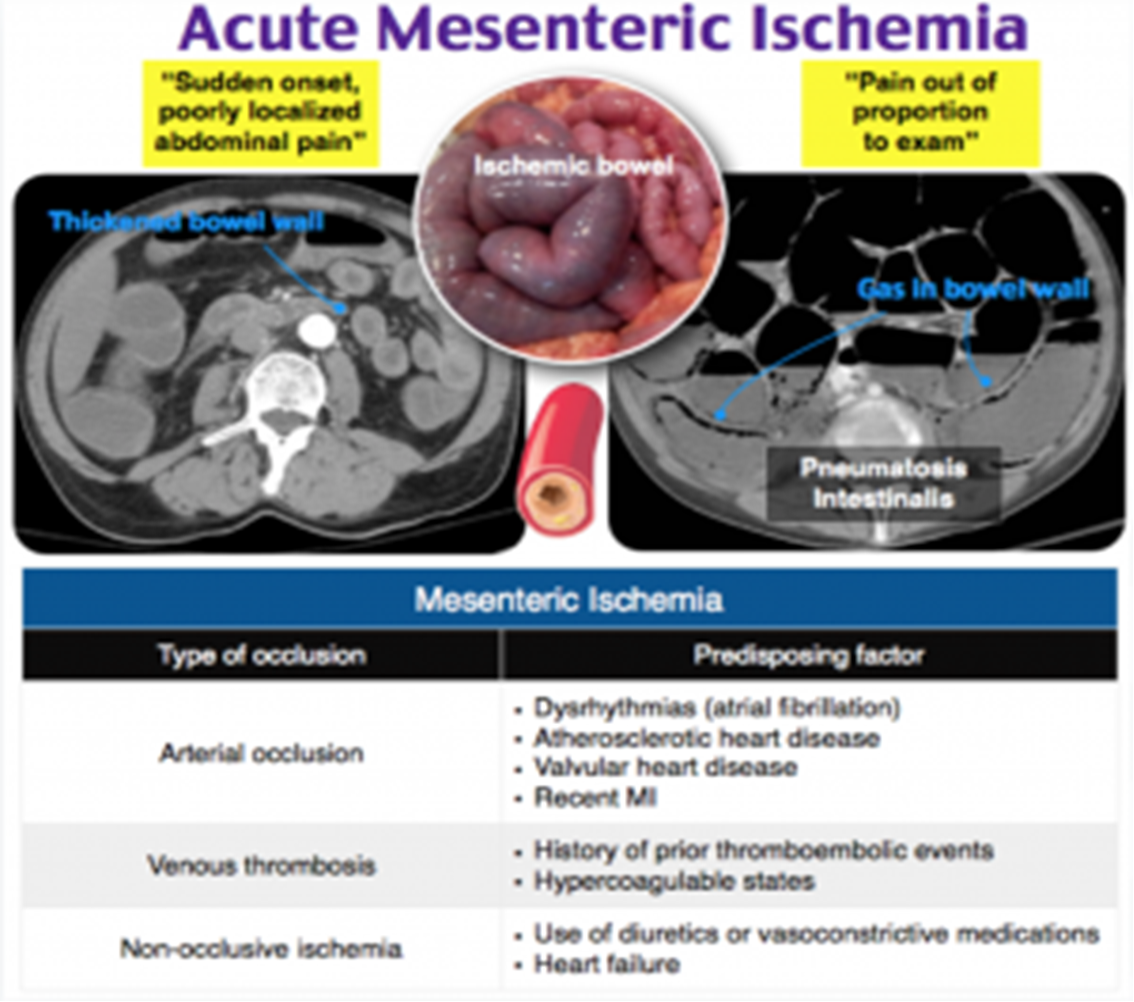
- Traditionally, mesenteric ischaemia presents with a generalised abdominal pain, out of proportion to the clinical findings, although it can often be more variable or subtle than this. The patient will typically complain of a diffuse and constant pain, with associated nausea and vomiting present in around 75% of cases
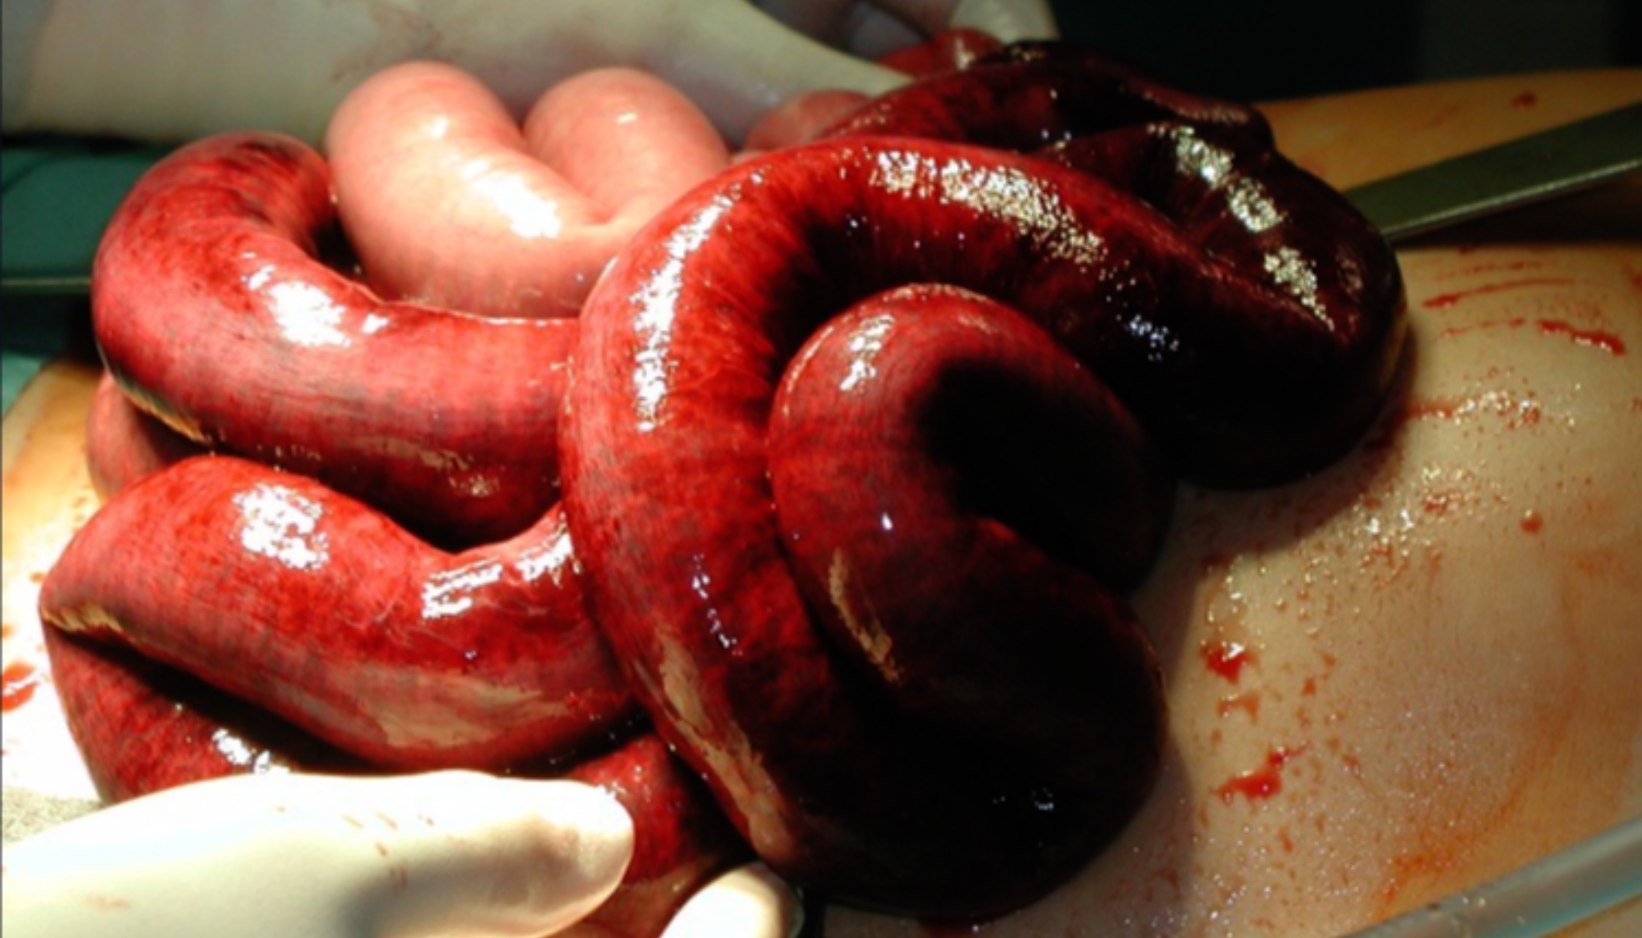
- On examination, the abdomen is often unremarkable* and the patient may find it difficult to localise the pain. However, remember late stage bowel ischaemia and necrosis can present as bowel perforation. → leading to Peritonitis → signs appear
- Importantly, take note of any potential embolic sources, such as AF, heart murmurs, or signs of previous valvular replacement surgery
*So should be careful when diagnosing Patient as Psychosomatic or malingering

*best way of diagnosing mesenteric ischemia is
CT scan
*once diagnosis it → do declotting by angiography →

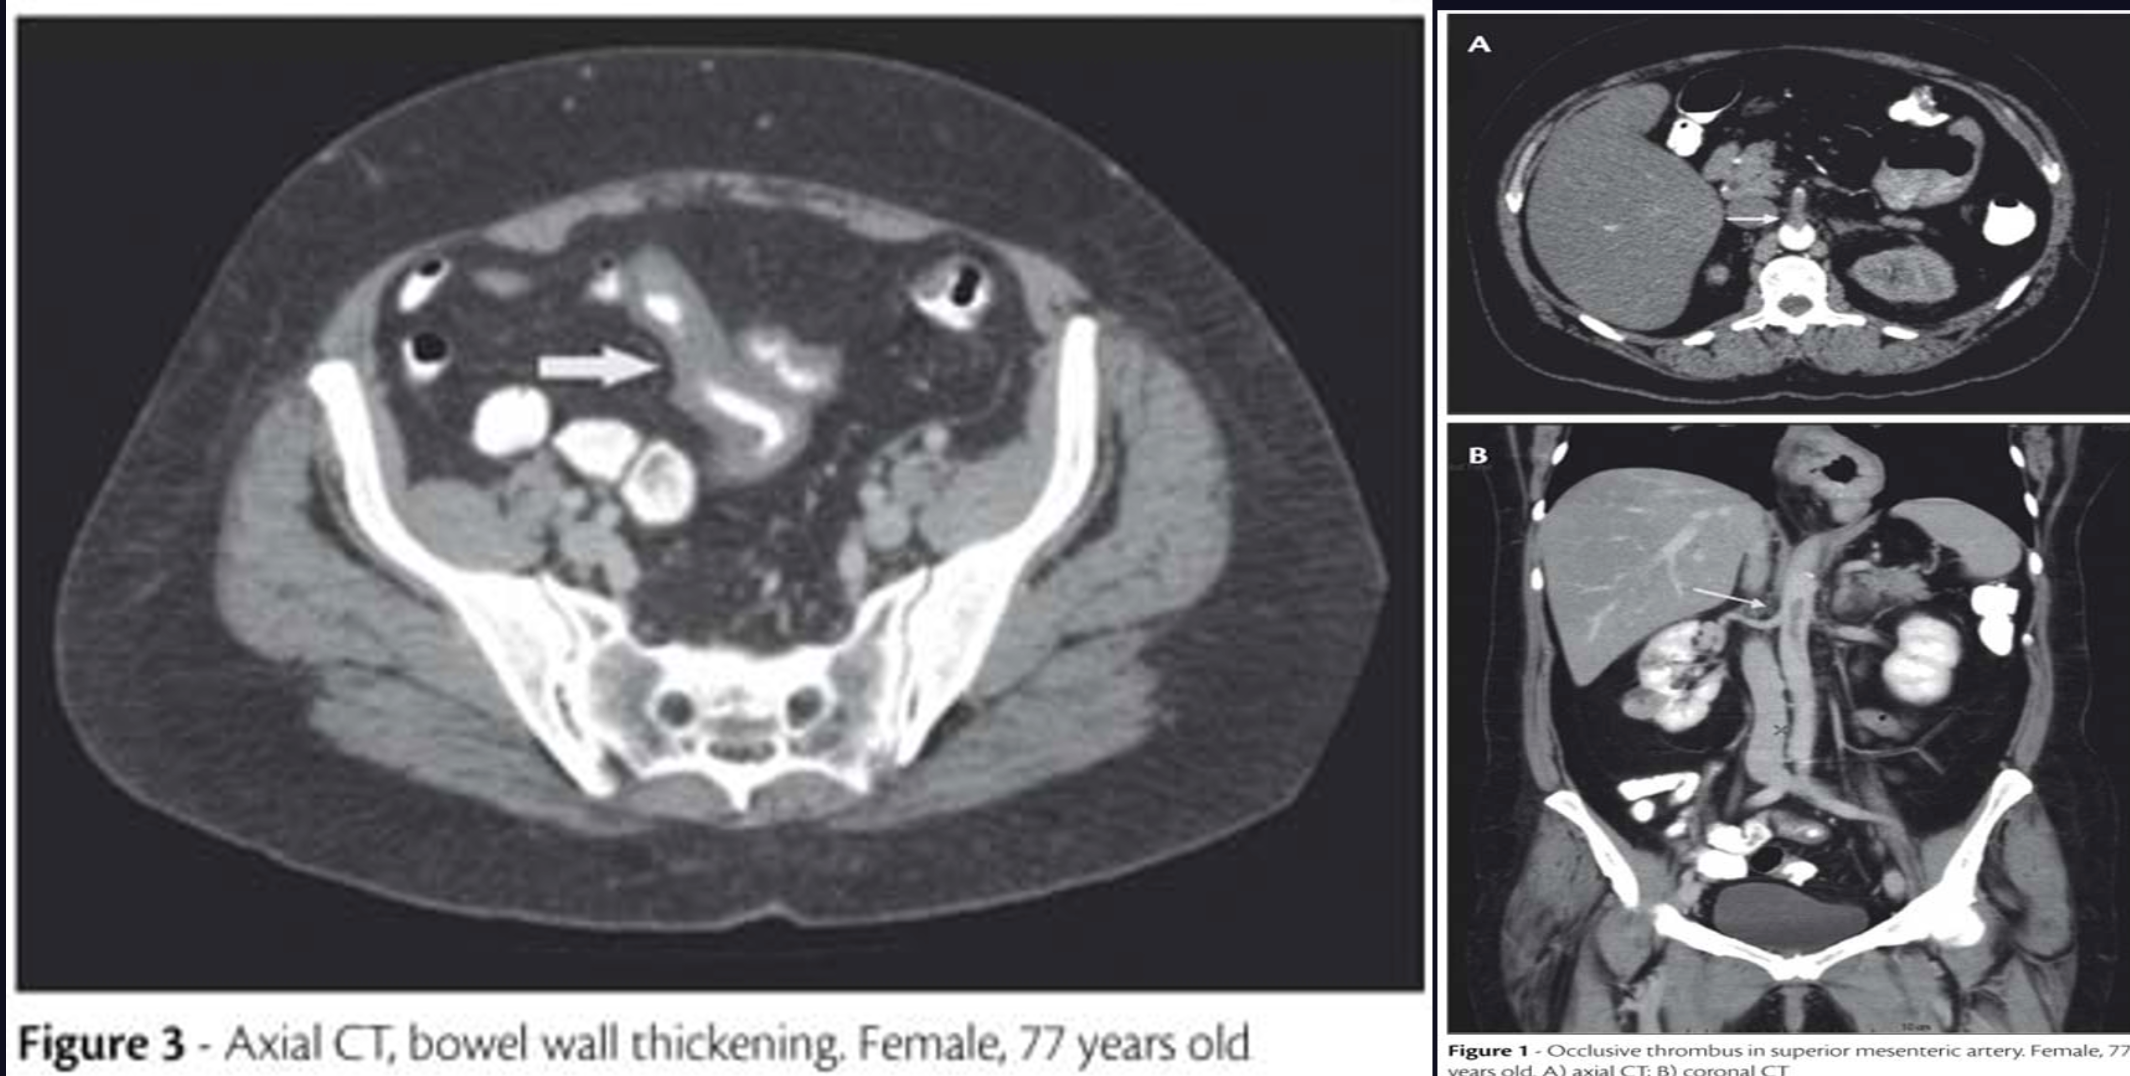
Figure 3 - Axial CT, bowel wall thickening. Female, 77 years old
go to femoral then to aorta then to SMA then dissolve the thrombus
(if present early)
*if late:
open abdomen and do resection of affected bowel
*if involve main Lessel ↓ poor prognosis -ent with Short bowel
Syntome →


Figure 1 - Occlusive thrombus in superior mesenteric artery. Female, 77 years old. A) axial CT; B) coronal CT
will be dependent on
→ No contrast indicating thrombus
*if its limited to a segment,
can do resection and anastomosis. but may miss
a part, so
after 2 days
from 1st surgery do 2nd look
operation.
↓ even if patient
not
complain in of anything
TPN
early option is bowel transplant
Case 6
mesenteric ischemia
The shift has just started, and your view of the waiting room reveals several patients with abdominal pain who checked in within twenty minutes of each other. The first patient is a 32 year-old female who presents with one week of worsening abdominal pain, which is non-localized. She has no medical problems, takes only oral contraceptives, and has a family history of venous thromboembolism. Her physical exam is normal, including vital signs, but she continues to complain of severe pain. You order a CBC, liver function panel, basic metabolic panel, urinalysis, and urine pregnancy test, while also ordering medications for nausea and pain.
Case 7
mesenteric ischemia
Your second patient is a 53 year-old male presenting with abdominal pain that worsens with eating and lasts several hours. He has no desire to eat due to worsening pain with food. He has a history of hypertension, peripheral vascular disease (PVD), chronic tobacco use, and diabetes. His exam is normal with no tenderness to palpation
Most physicians know the classic story of mesenteric ischemia, such as the 77 year-old male with a history of coronary disease, atrial fibrillation, coronary bypass, and hypertension who presents with severe abdominal pain but normal physical exam.
Table 1 – Differentiating the Four Types of Mesenteric Ischemia Y
| Cause | Symptoms | Presentation | Risk Factors | Incidence (%) | Mortality (%) |
|---|---|---|---|---|---|
| AE | Acute onset pain, Nausea/vomiting, Diarrhea, Bloody stool | Pain out of proportion, Distension, Tachycardia, Hypotension, Peritonitis | Atrial fibrillation, History of MI/CHF, Recent cardiac/vascular surgery | 34 (13-68) | 70 (27-100) |
| AT | Progressively worsening pain, Postprandial pain, Weight loss, Nausea/vomiting, Fear of food | Pain out of proportion, Distension, Tachycardia, Hypotension, Peritonitis | Chronic symptoms in 20-65%, History of CAD, Peripheral vascular disease, Tobacco use | 34 (17-64) | 66 (18-88) |
| Venous thrombosis | Insidious onset, Vague pain, Nausea/vomiting | Vague tenderness, GI bleeding in 10-16%, Peritonitis | Prior DVT/PE (50%), Recent abdominal surgery, Hypercoagulable state, OCP use | 13 (2-26) | 44 (25-69) |
| NOMI | Critically ill, Abdominal pain, Altered mental status, Diarrhea | Tenderness, Distension, Poor feeding/intolerance, Hypotension, Tachycardia | Recent cardiac surgery, CHF, Digitalis use, ESRD, Vasopressor use, Severe sepsis/septic shock | 19 (5-52) | 70 (50-83) |
Arterial embolism (AE), arterial thrombosis (AT), venous thrombosis, and non-occlusive (NOMI).
Table 2 – Performance of Laboratory Tests in AMI
| Laboratory Test | Sensitivity (%) | Specificity (%) |
|---|---|---|
| WBC | 80 | 50 |
| Lactate z | 86 | 44 |
| D-dimer | 96 | 40 |
| Urine I-FABP | 90 | 89 |
To diagnose mesenteric ischemia: 3 things.
CT angiography of the abdomen and pelvis with IV contrast is most commonly. (95% prediction)
*lactate if high indicate poor tissue perfusion scan help in diagnosis
urine intestinal fatty acid binding protein (I-FABP
③ CT scan
SURGERY
Acute Abdomen
The Dangerous Miss: Recognizing Acute Mesenteric Ischemia
80% of acute mesenteric ischemia cases result in mortality because of missed diagnosis. Here’s how to recognize the signs.
Mesenteric Ischemia
Traditionally, mesenteric ischaemia presents with a generalised abdominal pain, out of proportion to the clinical findings, although it can often be more variable or subtle than this. The patient will typically complain of a diffuse and constant pain, with associated nausea and vomiting present in around 75% of cases On examination, the abdomen is often unremarkable and the patient may find it difficult to localise the pain. However, remember late stage bowel ischaemia and necrosis can present as bowel perforation. Importantly, take note of any potential embolic sources, such as AF, heart murmurs, or signs of previous valvular replacement surgery
Small Bowel
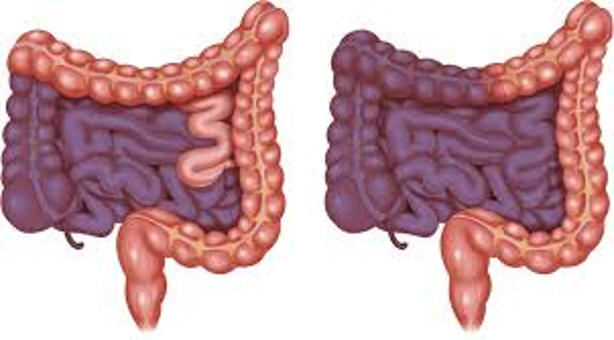
Mesenteric ischemia
-
Arterial or Venous
-
Acute or Chronic
-
Symptoms:
- Non-specific
- Severe abdominal pain out of proportion to the degree of abd. tenderness
- Diarrhoea (watery, bloody)
- Acute: Sudden abdominal pain, passage of altered blood, shock.
- Chronic: Abdominal angina, “food-fear”, weight loss or diarrhoea.
-
Signs:
- Abdominal tenderness
- Guarding
- Rigidity
- Symptoms are out of proportion to signs
Predisposing factors:
- Thrombophilia
- Hyper-viscosity
- Gut hypo-perfusion
- Shock (hypovolemic- cardiogenic-septic)
- Cardiac arrhythmia
Causes:
- Arterial:
- Arterial embolus : (most common-50%; heart; usually lodge distal to origin of the middle colic
- Recent MI- Atrial fib
- Polycythemia- SCD- DIC
- Arterial thrombosis
- Venous thrombosis : (5-15%) and 95% SMV
- Vasospasm (non-occlusive mesenteric ischemia – NOMI):
- usually in critically-ill pt.
- Receiving vasopressors.
Investigations:
- Labs:
- High WBC- High lactic acid- high amylase
- ABG (metabolic acidosis)
- AXR
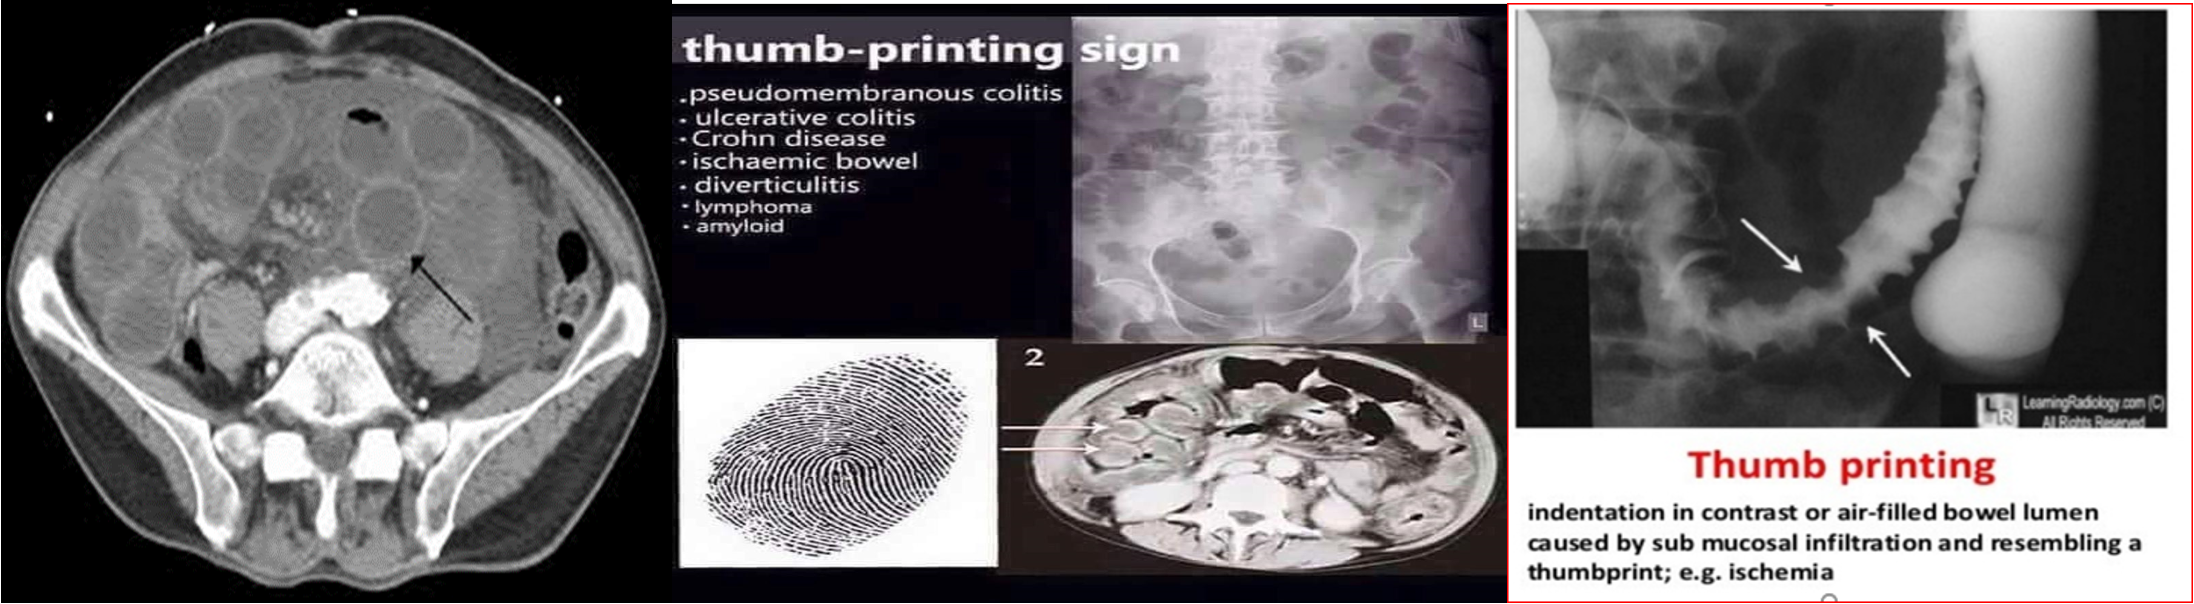
- Thickened, dilated gas-filled bowel
- Gas in bowel wall
- CT angiography
- Exclude other pathology
- Assess mesenteric vasculature, intestine & its mesentery
- Test of choice for acute mesenteric venous thrombosis
Treatment:
- Resuscitation,
- Golden hours
- Anticoagulation, & thrombolysis
- Surgical option:
- Bowel Resection,
- Embolectomy, thrombectomy
- Vascular bypass or Endarterectomy (If stable patient)
Surgical indications:
- signs of peritonitis :
- Necrotic : segmental resection
- Questionable viability: second look